Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Paediatric cataract
Cataract is the leading cause of childhood blindness in developing countries [S7]. Infantile cataract is one of the most treatable causes of lifelong visual impairment, but outcomes depend on early detection, timely surgery and years of refractive correction and amblyopia therapy [S6] [S8] [S11].
Key points - Examining all newborns with the red reflex test for congenital cataract and retinoblastoma is widely accepted, although supporting evidence is limited [S5]. - Late presentation, often from missed screening, causes deprivation amblyopia and irreversible visual loss [S11] [S12]. - An American Academy of Ophthalmology (AAO) assessment does not recommend IOL implantation at 6 months of age or younger, because visual axis opacities are more frequent than with aphakia; IOLs can be implanted safely after 6 months [S3]. - Visual axis opacification, glaucoma and amblyopia are the three most common complications; glaucoma develops long term in about a third of infants operated on [S6] [S11]. - Children from socioeconomically marginalised backgrounds have more delays and poorer adherence to amblyopia therapy, with worse outcomes [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Absent or abnormal red reflex, or leukocoria, in a baby or child [S5] [S7].
- Strabismus or nystagmus with a lens opacity: absence of nystagmus or strabismus predicts better outcomes, so their presence signals urgency and a worse prognosis [S6].
- Raised pressure, enlarging cornea or watering after childhood cataract surgery: glaucoma can appear years later [S1] [S6].
- Missed follow-up visits: late complications can occur decades later [S1].
Recognise it
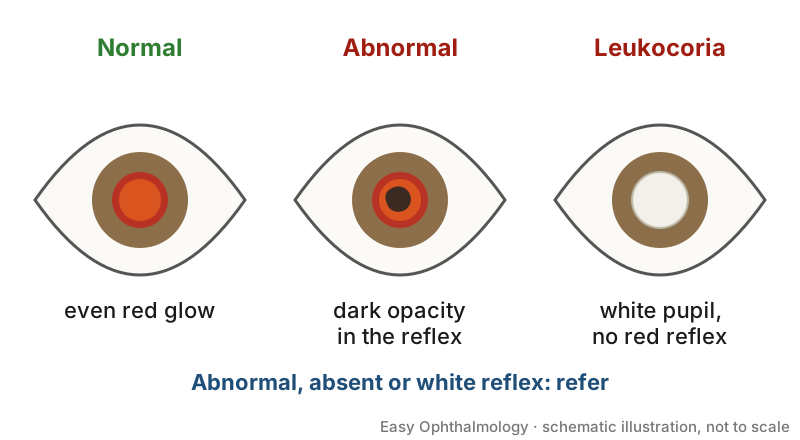
- Parents often bring children after noticing strabismus or leukocoria; many cases are found at routine checks, and the red reflex is absent on direct ophthalmoscopy [S7].
- Causes include genetic disorders, infections, metabolic diseases and trauma; about one-fourth of congenital cataracts are hereditary [S7] [S12].
- Cataract may occur with systemic disease, microphthalmia, microcornea or aniridia [S7].
- Persistent fetal vasculature and trauma are specific associated conditions [S11].
Confirm it
- In young babies the cataract type is determined by slit-lamp examination and examination under anaesthesia [S7].
- Cataract morphology can indicate the cause, guide surgery and inform prognosis [S6]; modern genetic tests can define the underlying aetiology [S11].
- Accurate biometry (axial length and keratometry) is essential before IOL implantation [S10].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Check the red reflex in every newborn and at child health visits [S5].
- Refer any abnormal red reflex, leukocoria or new squint in an infant the same day or within days (see Refer when) [S5] [S7].
- Explain to families that treatment continues for years after surgery; parental stress and health literacy affect outcomes [S8].
Tier B (general eye clinic)
- Confirm the opacity and refer to a paediatric cataract team; do not wait for the child to be older [S11] [S12].
- Support the long-term pathway after surgery: refractive correction and amblyopia therapy are critical, even months to years after cataract removal [S8]. The quality of orthoptic-refractive aftercare is the essential predictor of a good functional outcome [S4].
- Monitor for glaucoma, visual axis opacification and inflammation at every visit [S1] [S11].
Tier C (specialist centre)
- Timing. Many studies show the benefits of early surgery for infantile cataract [S6]; treatment must fall in the developmental window of the eye and visual pathway [S4].
- Optical correction in children 2 years or younger. IOLs gave visual outcomes similar to contact lenses or spectacles but more visual axis opacities, lower endothelial counts and, in infants under 6 months, large myopic shifts [S3]. Glaucoma and strabismus rates were similar across treatments [S3]. Contact lenses may be preferred under 6 months where available and practical [S6].
- IOL power. Formulas developed for adults give varying errors in children; Barrett Universal II and Kane appear more accurate than older formulas such as SRK/T. Undercorrection allows for myopic shift, but there is no consensus on formula or target refraction [S10]. Children may later need an IOL exchange or a large spectacle or contact lens correction [S3].
- Unilateral cataract. Only about 50% of eyes with unilateral infantile cataract reach better than 20/200; amblyopia therapy must continue until at least 8 years of age, but compliance was less than 30% of prescribed time [S2].
- Bilateral cataract. Contact lenses, IOLs or aphakic glasses can be used; outcomes are typically excellent unless glaucoma develops, which occurs in up to 30% [S2].
- Complications differ from adults, with stronger inflammation, posterior capsule opacification, lens reproliferation, pupillary membranes and, in infants, glaucoma [S1].
Refer when
| Situation | Urgency |
|---|---|
| Absent or abnormal red reflex or leukocoria in a newborn or infant | Urgent to a paediatric ophthalmologist; timing per your local service or specialist advice [EIC expert opinion] [S5] |
| Child with cataract and new squint, nystagmus or reduced vision | Urgent; timing per your local service or specialist advice [S6] |
| Red, painful eye or rising pressure after paediatric cataract surgery | Same-day [G1] [S1] |
| Child after cataract surgery missing refractive or amblyopia follow-up | Urgent recall and tracing; timing per your local service or specialist advice [S8] |
Pitfalls
- Skipping the newborn red reflex check [S5].
- Treating surgery as the end of care; aftercare quality predicts the outcome [S4].
- Implanting an IOL in infants 6 months or younger without weighing the higher opacification rate [S3].
- Using adult target refractions in a growing eye [S10].
- Discharging children from follow-up; glaucoma can occur late [S1] [S6].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2014 | Narrative literature review |
| [S2] | 2016 | Narrative review |
| [S3] | 2019 | AAO Ophthalmic Technology Assessment, 14 studies |
| [S4] | 2021 | Narrative review |
| [S5] | 2021 | Review of screening recommendations and systematic reviews |
| [S6] | 2022 | Narrative review |
| [S7] | 2022 | Narrative review |
| [S8] | 2023 | Narrative review of social determinants |
| [S9] | 2023 | Symposium summary |
| [S10] | 2025 | Narrative review |
| [S11] | 2025 | Comprehensive narrative review |
| [S12] | 2026 | Narrative review, Malaysia |
- Thin evidence. The triage sheet for this topic contained no randomised trials or meta-analyses; only the AAO assessment [S3] grades evidence. Findings from the Infant Aphakia Treatment Study and the Toddler Aphakia and Pseudophakia Study are referred to only indirectly through [S9].
- Reviews agree on early detection, early surgery and long-term amblyopia therapy, but differ on IOLs before 6 months: [S3] advises against, while [S6] notes good outcomes are possible and contact lenses may be preferred.
- Prevalence data from low-income countries are hard to determine [S6].
- Not covered by these sources: exact surgical timing in weeks, surgical technique (posterior capsulotomy, anterior vitrectomy), perioperative drug doses, and traumatic cataract management.
Related articles
- The white pupil (leukocoria): urgent assessment
- Amblyopia: patching, atropine and binocular treatment
- Childhood Glaucoma
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Whitman MC, Vanderveen DK Complications of pediatric cataract surgery. Seminars in ophthalmology. (2014). PubMed 25325868 · doi:10.3109/08820538.2014.959192
- [S2] Repka MX Visual Rehabilitation in Pediatric Aphakia. Developments in ophthalmology. (2016). PubMed 27043392 · doi:10.1159/000442501
- [S3] Lambert SR, Aakalu VK, Hutchinson AK, Pineles SL, Galvin JA, Heidary G, et al. Intraocular Lens Implantation during Early Childhood: A Report by the American Academy of Ophthalmology. Ophthalmology. (2019). PubMed 31230794 · doi:10.1016/j.ophtha.2019.05.009
- [S4] Lagrèze WA Treatment of congenital and early childhood cataract. Der Ophthalmologe : Zeitschrift der Deutschen Ophthalmologischen Gesellschaft. (2021). PubMed 33783620 · doi:10.1007/s00347-021-01370-z
- [S5] Jullien S Vision screening in newborns and early childhood. BMC pediatrics. (2021). PubMed 34496780 · doi:10.1186/s12887-021-02606-2
- [S6] Lenhart PD, Lambert SR Current management of infantile cataracts. Survey of ophthalmology. (2022). PubMed 35307324 · doi:10.1016/j.survophthal.2022.03.005
- [S7] Katre D, Selukar K The Prevalence of Cataract in Children. Cureus. (2022). PubMed 36381901 · doi:10.7759/cureus.30135
- [S8] Ahmad TR, de Alba Campomanes AG Pediatric Cataract: Disparately Blinding Globally and in the United States. Journal of binocular vision and ocular motility. (2023). PubMed 37931121
- [S9] Bothun ED Role of Intraocular Lens Implantation in Children. Journal of binocular vision and ocular motility. (2023). PubMed 37931124
- [S10] Rathod A, Khokhar S, Rani D Pediatric IOL power calculation: Factors and considerations. Indian journal of ophthalmology. (2025). PubMed 40007266 · doi:10.4103/ijo.ijo_1205_24
- [S11] Lloyd IC, Wilson ME, Trivedi RH, Biswas S, Ashworth JL, Green E, et al. Update on pediatric cataract surgery. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2025). PubMed 40780670 · doi:10.1016/j.apjo.2025.100229
- [S12] Karimmah W, Shatriah I Overview of paediatric cataract in Malaysia. The Medical journal of Malaysia. (2026). PubMed 42216740
Guidelines
- [G1] College of Optometrists (Guidance for Professional Practice). Annex 4 Urgency of referrals table (n.d.). https://www.college-optometrists.org/clinical-guidance/guidance/guidance-annexes/annex-4-urgency-of-referrals-table