Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Amblyopia: patching, atropine and binocular treatment
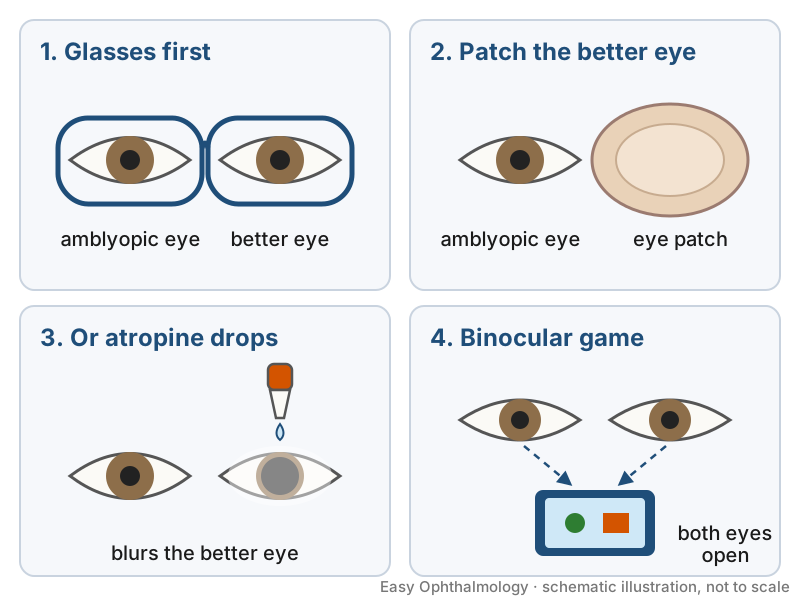
Amblyopia is impaired visual acuity in one or both eyes without a demonstrable abnormality of the visual pathway, and it is not immediately resolved by wearing glasses [S5]. It is the most common visual impairment of childhood [S8] and the leading cause of monocular reduced best-corrected vision in children [S12]. Glasses first, then patching or atropine, remain the evidence-based core of treatment, and treatment works best in young children [S9].
Key points - Correct refractive error first: glasses alone improve acuity with a large effect size in refractive and strabismic amblyopia [S4]. - In children aged 3 to 8 years, starting patching after 3 weeks of glasses was more successful than waiting 18 weeks (67% vs 54% success) in the EuPatch RCT [S8]. - Atropine penalisation appears as effective as patching, costs less and has better adherence, but causes light sensitivity and mild sound-eye blur more often (Cochrane review) [S5]. - Binocular (dichoptic) treatment gave gains similar to patching in the only RCT in a Cochrane review; long-term data are lacking [S7]. - Treatment is mostly effective under 7 years of age and patching should be tapered over at least 5 weeks, not stopped abruptly (Brazilian guideline) [S9].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Reduced vision with a visible ocular abnormality is not amblyopia. By definition amblyopia has no demonstrable abnormality of the visual pathway [S5]; trials required ophthalmic examination including the fundus before diagnosis [S7]. Do not start patching before the eye has been examined.
- Vision loss in the good eye during treatment. Atropine is associated with mild reduction in sound-eye acuity [S5]; reverse or worsening amblyopia was a reported non-serious harm of patching and digital treatment [S10]. Check both eyes at every visit.
- Older age at detection. Treatment is mostly effective under 7 years [S9], and the benefit of glasses falls with age [S4]. Do not delay treatment in a young child.
- Double vision. Double vision was reported as a non-serious harm of treatment [S10].
Recognise it
- Causes (amblyogenic factors): anisometropia, strabismus or both [S7] [S8]. Strabismus develops in approximately 5% to 8% of the general population [S3].
- Deficits beyond acuity: reduced stereoacuity and contrast sensitivity, and perceptual changes even in the sound eye [S9].
- Common working definition in trials: an interocular difference of 0.30 logMAR or more in best-corrected acuity [S8], or amblyopic eye acuity worse than 0.200 logMAR with the fellow eye 0.200 logMAR or better [S7].
Confirm it
- Use an age-appropriate acuity test and measure each eye separately [S7].
- Trials required cycloplegic refraction and an ophthalmic examination including the fundus [S7].
- A consensus decision-support tool from the Pediatric Eye Disease Investigator Group (PEDIG) gives testing methods, pass/refer criteria and monitoring schedules for children aged 3 to 17 years; where direct evidence was lacking its recommendations rest on committee consensus [S12].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Identify children with reduced acuity in one eye and refer for refraction and examination: in trials, treatment started only after cycloplegic refraction and an ophthalmic examination including the fundus [S7].
- Support families: adherence limits the effectiveness of treatment [S10].
Tier B (general eye clinic)
- Glasses first. Prescribe full refractive correction when indicated [S9]. Optical treatment alone gave a large positive effect size of 1.07 on acuity in a meta-analysis; effects were larger with longer wear and better starting acuity [S4]. In one trial, glasses alone improved acuity compared with no treatment (borderline significance) [S1].
- Do not wait too long before patching. In EuPatch (children 3 to 8 years, intensive patching of 10 hours a day, 6 days a week), early patching after 3 weeks of glasses succeeded in 107 of 159 (67%) vs 86 of 158 (54%) after 18 weeks of glasses [S8]. This conflicts with guidelines that recommend an extended glasses-only phase [S8] and with the meta-analysis favouring optical treatment first [S4].
- Patching or atropine. Adding occlusion improves vision when amblyopia persists in glasses, in refractive [S1] and strabismic [S3] amblyopia. Atropine penalisation is as effective as occlusion for acuity, with no difference in alignment or stereoacuity; it costs less and gives better adherence and quality of life, but more light sensitivity and mild sound-eye blur, while patching causes more skin, lid or conjunctival irritation [S5]. The Brazilian guideline restricts atropine to hyperopic children whose amblyopic eye sees better under cycloplegia than the fellow eye [S9].
- Dose. Patching regimens of 2 vs 6 hours (moderate amblyopia) and 6 hours vs full time (severe amblyopia) did not differ significantly in single trials [S1]. Atropine dosing is not covered by these abstracts: follow local formularies.
- When improvement stops. In children with stable residual amblyopia after at least 12 weeks of 2 hours daily patching, increasing to 6 hours gave 0.6 line more improvement at 10 weeks; 40% vs 18% gained 2 or more lines (PEDIG RCT) [S2].
- Stopping. Taper patching over at least 5 weeks [S9].
Tier C (specialist centre)
- Combinations. A 2026 network meta-analysis of 22 RCTs found that only full-time patching combined with video games (MD 0.27) and atropine combined with patching (MD 0.25) were significantly better than spectacles; other treatments did not differ significantly [S11].
- Binocular (dichoptic) treatment. A Cochrane review found one RCT (68 children): acuity gain at 16 weeks was similar to patching (0.21 vs 0.24 logMAR), adherence was lower (47% vs 90% achieved over 75% compliance), and no permanent diplopia occurred [S7]. A later phase 3 RCT of a dichoptic digital therapeutic plus glasses vs glasses alone in children aged 4 to 7 years found 1.8 vs 0.8 lines of gain at 12 weeks and was stopped early for success [S6]. These require devices and may not suit low-resource settings.
- Adherence interventions. A 2025 Cochrane review (18 studies) found very low-certainty evidence and could not conclude that behavioural, digital or alternative patching approaches improve objectively measured adherence [S10].
Refer when
| Situation | Urgency |
|---|---|
| Reduced acuity with any abnormal red reflex, fundus or media finding | Urgent; timing per your local service or specialist advice |
| New reduced acuity in one eye, or new squint, in a young child | Emergency referral, for a sudden new squint or double vision; routine referral to an eye clinic for gradually reduced acuity in one eye [EIC expert opinion] |
| Sound-eye acuity drops during patching or atropine | Urgent to the treating clinic; timing per your local service or specialist advice [S5] [S10] |
| No improvement after glasses and patching | Routine with a timeframe of next scheduled visit, to a specialist centre [S2] |
Pitfalls
- Patching before excluding structural disease [S5] [S7].
- Skipping glasses: optical treatment alone has a large effect [S4].
- Prolonged glasses-only periods in children who need patching [S8].
- Missing the sound eye's acuity on atropine [S5].
- Stopping patching abruptly [S9].
- Assuming games or rewards will fix poor adherence: the evidence is very low certainty [S10].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | Cochrane systematic review, 11 RCTs, no meta-analysis |
| [S2] | 2013 | Multicentre RCT, 169 children |
| [S3] | 2014 | Cochrane systematic review, 3 RCTs |
| [S4] | 2018 | Systematic review and meta-analysis, 29 papers |
| [S5] | 2019 | Cochrane systematic review, 7 trials, 1177 eyes |
| [S6] | 2022 | Phase 3 RCT, 105 children, stopped early |
| [S7] | 2022 | Cochrane systematic review, 1 RCT |
| [S8] | 2024 | Multicentre RCT, 334 children (Europe) |
| [S9] | 2024 | National guideline (Brazil) |
| [S10] | 2025 | Cochrane systematic review, 18 studies |
| [S11] | 2026 | Network meta-analysis, 22 RCTs |
| [S12] | 2026 | Consensus decision-support tool (PEDIG) |
- The optical-treatment meta-analysis had very high heterogeneity (I² = 96.65%) [S4].
- EuPatch was not masked and dropout was higher in the extended-glasses group (14% vs 6%) [S8]; its finding conflicts with the "glasses first for a long period" approach supported by [S4].
- No Cochrane review found trials in bilateral refractive amblyopia [S1]; no RCTs assessed partial occlusion or optical penalisation for strabismic amblyopia [S3].
- The dichoptic therapeutic trial compared against glasses alone, not patching [S6].
- Participants in the adherence review were mostly White, limiting generalisability [S10].
- Funding: EuPatch was funded by Action Medical Research, NIHR Clinical Research Network and Ulverscroft Foundation [S8]; the 2025 Cochrane review had no dedicated funding [S10].
- Not covered by these sources: atropine concentration and frequency, deprivation amblyopia (cataract, ptosis), treatment of adults, recurrence rates, and evidence from low-income settings.
Related articles
- Vision screening in children
- Childhood esotropia
- Refractive error in children and spectacle provision
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Taylor K, Powell C, Hatt SR, Stewart C Interventions for unilateral and bilateral refractive amblyopia. The Cochrane database of systematic reviews. (2012). PubMed 22513928 · doi:10.1002/14651858.cd005137.pub3
- [S2] Pediatric Eye Disease Investigator Group, Wallace DK, Lazar EL, Holmes JM, Repka MX, Cotter SA, et al. A randomized trial of increasing patching for amblyopia. Ophthalmology. (2013). PubMed 23755872 · doi:10.1016/j.ophtha.2013.04.008
- [S3] Taylor K, Elliott S Interventions for strabismic amblyopia. The Cochrane database of systematic reviews. (2014). PubMed 25051925 · doi:10.1002/14651858.cd006461.pub4
- [S4] Asper L, Watt K, Khuu S Optical treatment of amblyopia: a systematic review and meta-analysis. Clinical & experimental optometry. (2018). PubMed 29392811 · doi:10.1111/cxo.12657
- [S5] Li T, Qureshi R, Taylor K Conventional occlusion versus pharmacologic penalization for amblyopia. The Cochrane database of systematic reviews. (2019). PubMed 31461545 · doi:10.1002/14651858.cd006460.pub3
- [S6] Xiao S, Angjeli E, Wu HC, Gaier ED, Gomez S, Travers DA, et al. Randomized Controlled Trial of a Dichoptic Digital Therapeutic for Amblyopia. Ophthalmology. (2022). PubMed 34534556 · doi:10.1016/j.ophtha.2021.09.001
- [S7] Tailor V, Ludden S, Bossi M, Bunce C, Greenwood JA, Dahlmann-Noor A Binocular versus standard occlusion or blurring treatment for unilateral amblyopia in children aged three to eight years. The Cochrane database of systematic reviews. (2022). PubMed 35129211 · doi:10.1002/14651858.cd011347.pub3
- [S8] Proudlock FA, Hisaund M, Maconachie G, Papageorgiou E, Manouchehrinia A, Dahlmann-Noor A, et al. Extended optical treatment versus early patching with an intensive patching regimen in children with amblyopia in Europe (EuPatch): a multicentre, randomised controlled trial. Lancet (London, England). (2024). PubMed 38704172 · doi:10.1016/s0140-6736(23)02893-3
- [S9] Issaho DC, Rossetto JD, Curi I, Zagui R, Sá LC, Debert I, et al. Brazilian best practice guidelines for amblyopia diagnosis and management. Arquivos brasileiros de oftalmologia. (2024). PubMed 39607280 · doi:10.5935/0004-2749.2023-0281
- [S10] Chen DM, Han S, Summers A, Wang J, Rice M, Mallios J, et al. Interventions for improving adherence to amblyopia treatments in children. The Cochrane database of systematic reviews. (2025). PubMed 40600348 · doi:10.1002/14651858.cd015820.pub2
- [S11] Tan JH, Zhao W, Ren H, Zhang BW, Fu W, Tan QQ, et al. Comparison of the efficacy of unilateral amblyopia treatments: A systematic review and network meta-analysis. Survey of ophthalmology. (2026). PubMed 41314552 · doi:10.1016/j.survophthal.2025.11.013
- [S12] Summers AI, Hatch SW, Hatt SR, Wiecek EK, Hribar MR, Robinson JL, et al. Web-Based Amblyopia Decision Support Tool. JAMA ophthalmology. (2026). PubMed 42096234 · doi:10.1001/jamaophthalmol.2026.1095