Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Visual field testing and interpretation
Perimetry is central to glaucoma diagnosis and management [S6] [S8], is required in neuro-ophthalmic disorders of the afferent visual pathway [S9], and maps retinal function in diseases such as hydroxychloroquine retinopathy and age-related macular degeneration [S12]. Results vary between tests and between examiners' judgements, so reliable interpretation depends on good test strategy, a baseline, repeat testing and progression software [S2] [S6].
Key points - Repeat testing confirms or refutes apparent change; more frequent testing after diagnosis establishes a baseline and identifies rapid progressors [S6]. - Event analysis allows for expected local test-retest variability and trend analysis estimates overall rate of loss; clinicians agree only modestly when judging progression by eye [S2]. - SITA Faster cut test time in glaucoma patients by 59% to 68% and suits mild to moderate glaucoma, but shows milder defects than SITA Standard in more advanced disease [S3] [S8]. - The 10-2 test is more sensitive to central and advanced loss and may be underused [S8] [S11]. - Home and tablet perimetry is promising but its accuracy in real life is uncertain [S4] [S5].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings that need urgent action
- A defect respecting the vertical meridian (homonymous or bitemporal). Patterns respecting the vertical meridian point to retrochiasmal or chiasmal damage, whereas glaucoma respects the horizontal meridian [S7]; arrange urgent neuro-ophthalmic assessment and imaging.
- Rapid progression on repeat fields. May need more aggressive management [S6].
- Central field involvement in glaucoma. Affects reading, driving and walking [S11]; check with a 10-2 test [S8].
- Field loss in a driver. Peripheral loss causes driving difficulty, especially lane keeping, leading to driving cessation [S7].
- Paracentral scotomas in a patient on hydroxychloroquine. Automated perimetry is critical for detecting them [S12].
Recognise it: patterns and their meaning
- Field loss follows specific patterns depending on cause and can be tracked for progression [S9] [S10].
- Glaucoma and retrochiasmal damage typically spare central vision at first [S7].
- Peripheral field loss affects 13% of people over 65 and impairs driving, reading, face recognition and navigation [S7].
- In advanced glaucoma, structural and functional tests reach technical limits that can delay detection of true progression [S1].
Confirm it: is the field reliable and real?
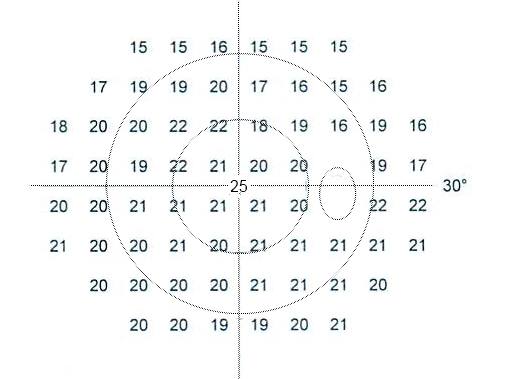
- Reliability. Patient fatigue, response variability and unreliable results are common challenges [S12]. The technician has an important role in supervising the test [S8]. Fogging of the trial lens by a face mask can cause inferior rim artefacts [S8].
- Strategy. In 59 subjects tested with the 24-2 program, SITA Faster saved 68% of test time in glaucoma patients, with strong agreement with SITA Standard that was lower in advanced glaucoma [S3].
- Pattern. The 24-2C may help detect early disease and the 10-2 advanced loss [S8]. 10-2 testing adds information in high myopia, disc haemorrhage and advanced cases [S11].
- Repeat any new defect before acting on it [S6].
- Structure-function. Combining OCT with automated perimetry improves care in neuro-ophthalmic disorders [S9].
Manage it: testing and acting at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Simple tools such as the Amsler grid and kinetic methods identify large or central defects [S12]. Some older perimetric techniques are often still effective, and newer technologies may cost more [S10].
- Tablet perimetry has the potential to be a low-cost, portable screening method testing the central 30 degrees [S5]; validation is still limited [S4].
- Refer any suspected field defect (see table).
Tier B (general eye clinic)
- Use standard automated perimetry where available; a faster strategy allows more fields to be done, as guidelines recommend [S3].
- Supervise tests and repeat unreliable or abnormal fields [S6] [S8].
- Build a baseline of several fields early after diagnosis [S6].
- Choose the method to suit the disease and patient; newer non-contact objective methods may help test children and the infirm [S10].
Tier C (specialist centre)
- Use event and trend progression analysis together [S2] [S6].
- Add 10-2 testing in advanced disease and when central damage is likely [S11].
- Microperimetry gives localised sensitivity maps in macular disease; frequency-doubling technology may reveal early neural deficits in diabetic retinopathy [S12].
- Home perimetry may detect progression earlier and reduce clinic burden [S8], but diagnostic studies had high risk of bias, with sensitivity from 54% (mild) to 91% (moderate to severe glaucoma) and specificity 50% to 100% [S4].
- AI shows high sensitivity and specificity compared with experts for detecting abnormality and progression; clinicians still interpret and act [S8].
- Use field results to direct low-vision rehabilitation [S9].
Refer when
| Situation | Urgency |
|---|---|
| New homonymous, bitemporal or other vertically aligned defect [S7] | Same-day, through the stroke pathway where stroke is possible [EIC expert opinion] |
| Glaucoma with confirmed rapid field progression [S6] | Urgent to a glaucoma service; timing per your local service or specialist advice |
| Repeatable glaucomatous field defect, new diagnosis | Routine; timing per your local service or specialist advice |
| Paracentral loss on hydroxychloroquine screening [S12] | Routine to retina and the prescriber; timing per your local service or specialist advice |
Pitfalls
- Acting on a single abnormal field without repeating it [S6].
- Judging progression by eye alone [S2].
- Comparing SITA Faster and SITA Standard results as equivalent in advanced disease [S3] [S8].
- Relying on 24-2 alone when central damage is likely [S11].
- Missing mask or lens artefacts [S8].
- Assuming newer perimeters are better: they cost more and may not reach the desired accuracy [S10].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2016 | Narrative review |
| [S2] | 2017 | Narrative review |
| [S3] | 2022 | Randomised cross-sectional comparison, 59 subjects |
| [S4] | 2022 | Systematic review, 18 studies |
| [S5] | 2022 | Narrative review |
| [S6] | 2023 | Narrative review |
| [S7] | 2023 | Narrative review |
| [S8] | 2023 | Narrative review |
| [S9] | 2024 | Narrative review |
| [S10] | 2024 | Narrative review |
| [S11] | 2024 | Narrative review |
| [S12] | 2025 | Narrative review |
- The evidence on this sheet is thin: one systematic review [S4], one small comparison study [S3] and narrative reviews. No guideline or RCT of testing strategies was available.
- Home perimetry studies were mostly in clinic or laboratory settings with selected populations [S4].
- Not covered by these sources: numeric reliability-index cut-offs (fixation losses, false positives), glaucoma hemifield test and mean deviation thresholds, staging systems, recommended testing frequency in number of fields per year, and confrontation field technique.
Related articles
- Visual Pathway Lesions and Field Defects
- Primary Open-Angle Glaucoma: Diagnosis and Treatment Targets
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] de Moraes CG, Liebmann JM, Medeiros FA, Weinreb RN Management of advanced glaucoma: Characterization and monitoring. Survey of ophthalmology. (2016). PubMed 27018149 · doi:10.1016/j.survophthal.2016.03.006
- [S2] Aref AA, Budenz DL Detecting Visual Field Progression. Ophthalmology. (2017). PubMed 29157362 · doi:10.1016/j.ophtha.2017.05.010
- [S3] Rodríguez-Agirretxe I, Loizate E, Astorkiza B, Onaindia A, Galdos-Olasagasti L, Basasoro A Validation of the SITA faster strategy for the management of glaucoma. International ophthalmology. (2022). PubMed 35072855 · doi:10.1007/s10792-022-02232-6
- [S4] Daka Q, Mustafa R, Neziri B, Virgili G, Azuara-Blanco A Home-Based Perimetry for Glaucoma: Where Are We Now? Journal of glaucoma. (2022). PubMed 35394454 · doi:10.1097/ijg.0000000000002022
- [S5] Ichhpujani P, Dhillon H Spotlight on iPad Visual Field Tests Efficacy. Clinical ophthalmology (Auckland, N.Z.). (2022). PubMed 35818511 · doi:10.2147/opth.s340508
- [S6] Chen RI, Gedde SJ Assessment of visual field progression in glaucoma. Current opinion in ophthalmology. (2023). PubMed 36378107 · doi:10.1097/icu.0000000000000932
- [S7] Okrent Smolar AL, Gagrani M, Ghate D Peripheral visual field loss and activities of daily living. Current opinion in neurology. (2023). PubMed 36409221 · doi:10.1097/wco.0000000000001125
- [S8] Lee GA, Kong GYX, Liu CH Visual fields in glaucoma: Where are we now? Clinical & experimental ophthalmology. (2023). PubMed 36751125 · doi:10.1111/ceo.14210
- [S9] Banc A, Kedar S Interpretation of the Visual Field in Neuro-ophthalmic Disorders. Current neurology and neuroscience reports. (2024). PubMed 38289405 · doi:10.1007/s11910-024-01332-3
- [S10] Rai BB, Sabeti F, Carle CF, Maddess T Visual Field Tests: A Narrative Review of Different Perimetric Methods. Journal of clinical medicine. (2024). PubMed 38730989 · doi:10.3390/jcm13092458
- [S11] Du KH, Kamalipour A, Moghimi S Central visual field in glaucoma: An updated review. Taiwan journal of ophthalmology. (2024). PubMed 39430344 · doi:10.4103/tjo.tjo-d-24-00042
- [S12] Kim KE, Ahn SJ Visual Field Examinations for Retinal Diseases: A Narrative Review. Journal of clinical medicine. (2025). PubMed 40806887 · doi:10.3390/jcm14155266