Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Sudden painless vision loss: triage
Acute vision loss is a time-critical presentation that must be triaged quickly to separate benign causes from ophthalmic and neurological emergencies, often by non-ophthalmic clinicians [S11]. Acute retinal artery occlusion presents with sudden, painless monocular vision loss and is equivalent to a cerebral stroke [S12]. Giant cell arteritis (GCA) can cause irreversible loss in one or both eyes [S6].
Key points - Treat sudden painless monocular vision loss as a possible stroke: retinal artery occlusion needs a standard stroke evaluation [S12]. - Acute cerebral ischaemia was found on MRI in 30% of patients with central retinal artery occlusion (CRAO) and 25% with branch occlusion (BRAO) [S8]. - Transient monocular vision loss (amaurosis fugax) is a transient ischaemic attack and needs the same urgent work-up as stroke [S9]. - Stroke risk is highest in the first few days; eye care professionals should refer immediately to a stroke centre rather than performing further tests themselves [S7]. - Consider GCA; vision loss is its most feared and irreversible complication [S6].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Sudden painless monocular loss (possible CRAO or BRAO) [S12].
- Transient monocular loss, which portends possible future vision loss and stroke [S4] [S9].
- Features of GCA [S6] [S11].
- Other conditions needing immediate specialist involvement: acute angle-closure glaucoma, retinal detachment and optic neuritis [S11].
- Cardiovascular risk factors in a patient with retinal artery occlusion: atrial fibrillation, heart failure, valvular heart disease, dyslipidaemia and smoking were linked to stroke [S10].
Recognise it
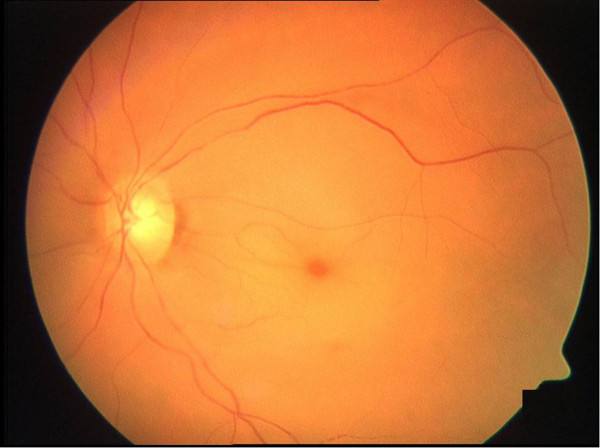
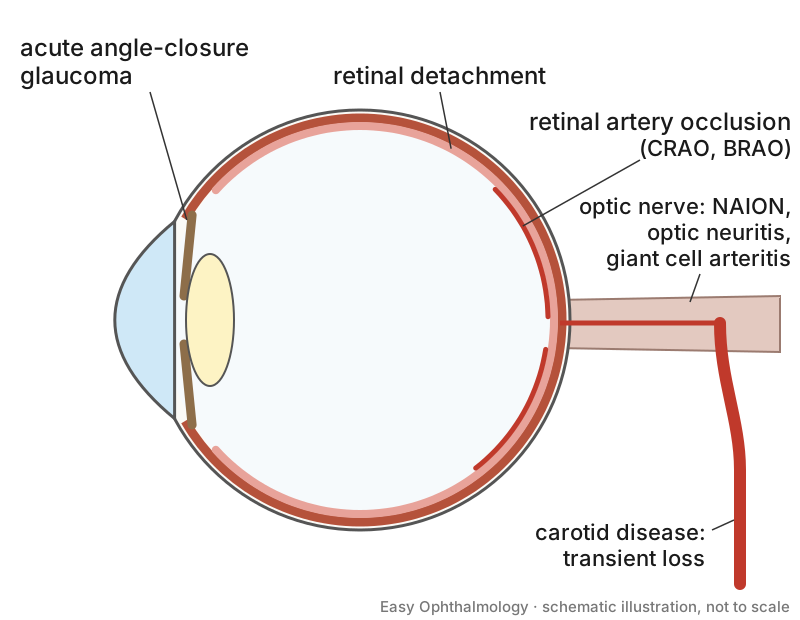
- A five-step approach: (1) one eye or both, (2) painful or painless, (3) targeted history, (4) focused chairside examination for red flags, (5) action by escalation, investigation and referral [S11].
- Duration: transient loss lasts less than 24 hours and persistent loss more than 24 hours [S2].
- CRAO: over three-quarters of patients have profound loss, with acuity of 20/400 or worse [S1]. CRAO includes non-arteritic, transient non-arteritic, cilioretinal-sparing and arteritic forms [S1].
- Non-arteritic anterior ischaemic optic neuropathy (NAION) is the most common cause of acute optic nerve injury in adults and older people [S5].
- Transient loss may reflect carotid occlusion or thromboembolism, or a benign cause such as migraine or vasospasm [S4].
Confirm it
- Fundus examination confirms retinal artery occlusion, helped by fundus photography and OCT [S12].
- Do not delay transfer for further eye tests in acute retinal arterial ischaemia [S7].
- Stroke work-up: urgent brain MRI with diffusion-weighted imaging, vascular imaging and clinical assessment are recommended for transient loss, BRAO and CRAO [S7]. Imaging of the brain and the extracranial and intracranial vessels is the cornerstone of TIA work-up, with cardiac and blood tests [S9].
- Most acute cerebral ischaemia in these patients is asymptomatic: 22% of CRAO and 29% of BRAO cohorts had silent lesions [S8].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Act at once. Educate patients to call emergency services for acute vision loss, so they are taken straight to a facility linked to a stroke centre [S12].
- Refer immediately any suspected retinal arterial ischaemia or transient monocular loss to a stroke service [S7].
- Possible GCA: refer urgently through a fast-track pathway where available [S6]; see the GCA article for treatment.
Tier B (general eye clinic)
- Confirm the diagnosis on fundus examination and transfer without further testing [S7] [S12].
- "Conservative treatments" such as anterior chamber paracentesis, ocular massage and haemodilution have no benefit and should not be pursued [S12].
- NAION: no widely accepted evidence-based treatment exists; measures to protect the other eye have only theoretical bases [S5]. Look for systemic associations [S5].
Tier C (specialist centre)
- Thrombolysis: meta-analyses and expert reviews suggest a possible treatment effect of IV tPA within 4.5 hours or intra-arterial tPA within 6 hours of vision loss in CRAO; trials are ongoing and there are no widely accepted therapies yet [S12]. No therapy is guideline-endorsed [S1].
- Secondary prevention of cerebral ischaemia is the mainstay of management [S4] [S9]: antiplatelet therapy, healthy lifestyle and control of hypertension, dyslipidaemia and diabetes, plus specific treatment of symptomatic carotid stenosis greater than 50%, aortic arch atheroma or atrial fibrillation [S9].
- Carotid stenosis: after carotid-related symptoms, pooled stroke risk with active follow-up was 6.0% at 2 to 3 days, 10.9% at 7 days and 17.6% at 14 days, supporting surgery as soon as possible [S3].
- Hospital admission is recommended for patients presenting within 72 hours of transient symptoms who meet high-risk criteria [S4].
Refer when
| Situation | Urgency |
|---|---|
| Sudden painless monocular vision loss (suspected CRAO or BRAO) | Immediate: emergency transfer to a stroke centre; thrombolysis may be considered within 4.5 hours [S7] [S12] |
| Transient monocular vision loss | Immediate stroke-pathway assessment; stroke risk is highest in the first few days [S7] [S9] |
| Suspected GCA | Same-day [S6] |
| Suspected acute angle closure, retinal detachment or optic neuritis | Immediate specialist involvement [S11] |
| NAION, stable | Urgent to a neuro-ophthalmology or eye service to look for systemic associations; timing per your local service or specialist advice [S5] |
Pitfalls
- Doing ocular massage or paracentesis instead of transferring the patient [S12].
- Dismissing transient loss because vision has recovered [S4] [S9].
- Delaying transfer for additional eye investigations [S7].
- Forgetting cardiac risk factors and silent brain infarcts in retinal artery occlusion [S8] [S10].
- Missing GCA as the cause [S6].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2013 | Narrative review (CRAO) |
| [S2] | 2015 | Narrative review (primary care) |
| [S3] | 2015 | Systematic review, 10 studies, 2634 patients |
| [S4] | 2016 | Narrative review (transient vision loss) |
| [S5] | 2016 | Narrative review (NAION) |
| [S6] | 2013 | Narrative review (GCA) |
| [S7] | 2018 | Expert review of guidelines |
| [S8] | 2020 | Systematic review and meta-analysis (MRI) |
| [S9] | 2022 | Review of guidelines (TIA and amaurosis fugax) |
| [S10] | 2025 | Systematic review and meta-analysis, 46 studies, 101,952 patients |
| [S11] | 2026 | Narrative review |
| [S12] | 2026 | Narrative review |
- Two meta-analyses support the stroke association [S8] [S10]; management advice is from expert and guideline reviews [S7] [S9] [S12].
- Thrombolysis for CRAO remains unproven; RCTs of tPA have been investigated and new trials are ongoing [S1] [S12].
- The stroke-centre pathway assumes access to MRI and stroke services; the sources do not address settings without them.
- Not covered by these sources: retinal vein occlusion, vitreous haemorrhage, GCA treatment doses, and functional or non-organic vision loss.
Related articles
- Central Retinal Artery Occlusion: An Ocular Stroke
- Rhegmatogenous Retinal Detachment
- Giant Cell Arteritis
- Retinal Vein Occlusion
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Varma DD, Cugati S, Lee AW, Chen CS A review of central retinal artery occlusion: clinical presentation and management. Eye (London, England). (2013). PubMed 23470793 · doi:10.1038/eye.2013.25
- [S2] Bagheri N, Mehta S Acute Vision Loss. Primary care. (2015). PubMed 26319342 · doi:10.1016/j.pop.2015.05.010
- [S3] Tsantilas P, Kühnl A, Kallmayer M, Knappich C, Schmid S, Kuetchou A, et al. Stroke risk in the early period after carotid related symptoms: a systematic review. The Journal of cardiovascular surgery. (2015). PubMed 26399273
- [S4] Pula JH, Kwan K, Yuen CA, Kattah JC Update on the evaluation of transient vision loss. Clinical ophthalmology (Auckland, N.Z.). (2016). PubMed 26929593 · doi:10.2147/opth.s94971
- [S5] Gaier ED, Torun N The enigma of nonarteritic anterior ischemic optic neuropathy: an update for the comprehensive ophthalmologist. Current opinion in ophthalmology. (2016). PubMed 27585212 · doi:10.1097/icu.0000000000000318
- [S6] Patil P, Karia N, Jain S, Dasgupta B Giant cell arteritis: a review. Eye and brain. (2013). PubMed 28539785 · doi:10.2147/eb.s21825
- [S7] Biousse V, Nahab F, Newman NJ Management of Acute Retinal Ischemia: Follow the Guidelines! Ophthalmology. (2018). PubMed 29716787 · doi:10.1016/j.ophtha.2018.03.054
- [S8] Fallico M, Lotery AJ, Longo A, Avitabile T, Bonfiglio V, Russo A, et al. Risk of acute stroke in patients with retinal artery occlusion: a systematic review and meta-analysis. Eye (London, England). (2020). PubMed 31527762 · doi:10.1038/s41433-019-0576-y
- [S9] Mbonde AA, O'Carroll CB, Dulamea OA, Anghel D, Chong BW, Dumitrascu OM Current Guidelines on Management of Amaurosis Fugax and Transient Ischemic Attacks. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2022). PubMed 35213421 · doi:10.1097/apo.0000000000000511
- [S10] Pothikamjorn T, Charnnarong C, Susantitaphong P, Jariyakosol S Incidence and risk factors associated with ischemic cerebrovascular disease in patients with retinal artery occlusion: a systematic review and meta-analysis. Scientific reports. (2025). PubMed 41006752 · doi:10.1038/s41598-025-18419-7
- [S11] Maher C, Guo B, Yek J A Five-Step Approach to Acute Vision Loss: A Practical Narrative Review for Clinicians. Clinical ophthalmology (Auckland, N.Z.). (2026). PubMed 41782901 · doi:10.2147/opth.s590753
- [S12] Bénard-Séguin É, Mac Grory B, Newman NJ, Biousse V Acute retinal artery occlusions. Handbook of clinical neurology. (2026). PubMed 42217977 · doi:10.1016/b978-0-443-22212-2.00003-3