Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Biometry and IOL power calculation
Intraocular lens (IOL) power calculation combines measured corneal power and axial length with a formula, and the choice of formula is an important part of cataract surgery [S7] [S9]. Errors cause refractive surprises that are hard to correct, especially in short, long, keratoconic and post-refractive-surgery eyes [S1] [S4] [S11].
Key points - Swept-source optical biometers measure axial length successfully in most cataracts, but failure rates reach 38.49% in some studies, mostly in mature white or grade IV or higher cataracts [S5]. - Where optical biometry is not available, keratometry with immersion ultrasound biometry is advised as the preoperative standard for humanitarian surgery in developing countries [S10]. - Barrett Universal II, Kane and PEARL-DGS are most often reported as the most precise modern formulas [S7]; in eyes of 26 mm or longer, Olsen, Kane and EVO ranked highest, without statistically significant differences [S8]. - After myopic LASIK or PRK, refraction is less accurate even with the best methods; averaging several methods gave the best results [S4]. - Optimising and personalising lens constants improves prediction accuracy [S9].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Previous corneal refractive surgery. Standard keratometry with a standard formula gave a universally hyperopic error and only 8% to 40% of eyes within 0.5 D of target [S4].
- Keratoconus. Hyperopic outcomes increase with steeper keratometry, and accuracy is poor at keratometry of 50.0 D or more [S11].
- Extreme axial length. Short (under 22 mm) and long (26 mm or more) eyes need formula choice by evidence, not habit [S1] [S8].
- Dense or white cataract. Optical biometry may fail [S5].
- Children. Formula accuracy differs from adults [S6].
Recognise it: who needs extra care
- Short eyes, long eyes, keratoconus, eyes having combined endothelial keratoplasty and cataract surgery, and post-refractive eyes are the main challenging groups [S11].
- In combined Descemet membrane endothelial keratoplasty and cataract surgery, target more myopia, ranging from -0.75 to -1.0 D [S11].
Confirm it: measurement
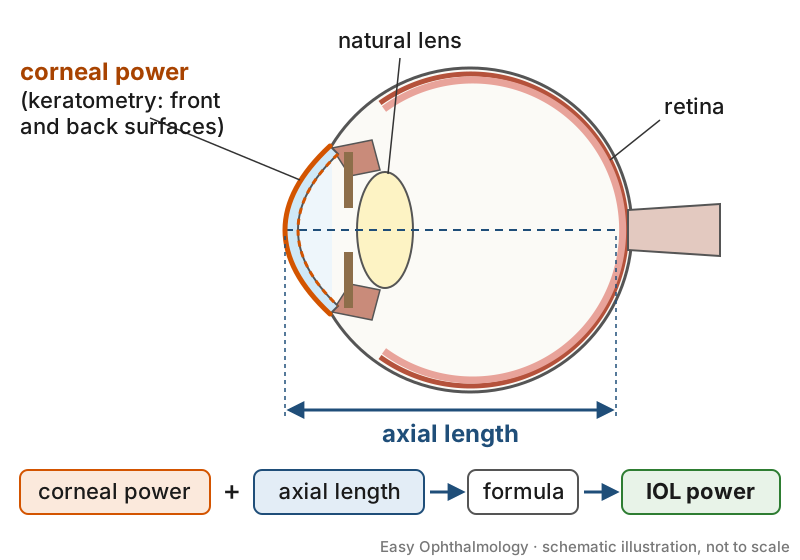
- Optical biometry. Swept-source biometers have an accuracy of 0.01 to 0.02 mm and are described as the state-of-the-art method [S9]. They measure axial length in dense cataracts more often than common biometers [S2] [S5].
- Posterior cornea. Measuring both anterior and posterior corneal power is increasingly recognised as important [S9].
- Contact lenses. Soft contact lenses may not need removal more than 2 days before biometry [S2].
- Ultrasound. Immersion ultrasound biometry with keratometry is recommended for missions in developing countries [S10].
- Toric alignment. In an RCT of 132 eyes, automated image-guided marking gave a smaller axis error (3.63 vs 8.29 degrees) than manual marking [S3].
Manage it: choosing the IOL power
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Tier A staff do not calculate IOL power. Record any history of refractive surgery, keratoconus, contact lens wear or very high spectacle power and pass it to the surgical team, as these change the calculation [S2] [S4] [S11].
Tier B (general eye clinic)
- Measure well. Use keratometry with immersion ultrasound where optical biometry is unavailable [S10]; use optical biometry where available [S9].
- Use a modern formula. Third- and fourth-generation formulas are being replaced by more accurate ones; Barrett Universal II is most often reported as precise among vergence formulas [S7] and may be used confidently for most eyes [S2].
- Short eyes (under 22 mm). A meta-analysis of 10 observational studies (1161 eyes) found Haigis superior to Hoffer Q, SRK/T and SRK II; SRK II performed worst [S1]. Among newer formulas, PEARL-DGS achieved the highest percentage within 0.5 D in most studies, and one review reports the ZEISS AI IOL calculator produced the best outcomes [S7] [S11].
- Long eyes (26 mm or more). A network meta-analysis of 10 studies (1016 eyes) ranked Olsen, Kane and EVO highest for prediction error within 0.25 D, with considerable uncertainty; Wang-Koch adjusted Holladay 1 also performed well [S8] [S11].
- Optimise constants. Audit outcomes and personalise lens constants to correct systematic bias from devices, formulas and the surgeon [S9].
Tier C (specialist centre)
- Post-myopic LASIK or PRK. Methods needing pre-refractive keratometry and refraction are no longer the gold standard; methods needing no history had MAEs of 0.42 to 0.94 D, and averaging several methods gave the highest proportion (66% to 68%) within 0.5 D [S4]. Newer formulas that use posterior corneal data include Barrett True-K TK, PEARL-DGS, EVO 2.0 and Hoffer QST; select power by consensus of several formulas [S11]. Counsel patients about the reduced accuracy [S4].
- Keratoconus. Keratoconus-specific formulas (Barrett True K for keratoconus, Kane keratoconus) exist [S11].
- Children. A network meta-analysis of 13 studies (1781 eyes) ranked Barrett Universal II, SRK/T and Holladay 1 as most accurate; Barrett Universal II tends to perform better in older children, and SRK II performed worst [S6].
Refer when
| Situation | Urgency |
|---|---|
| Previous LASIK, PRK or keratoconus in a patient listed for cataract surgery | Routine, before listing, to a centre able to do advanced calculations; timing per your local service or specialist advice [S4] [S11] |
| Axial length cannot be measured or eyes differ markedly in axial length or keratometry | Routine, for repeat biometry before surgery; timing per your local service or specialist advice [S5] |
| Child with cataract needing IOL power calculation | Urgent to a paediatric cataract service; timing per your local service or specialist advice [S6] |
| Unexpected large refractive error after surgery | Routine to the operating surgeon; timing per your local service or specialist advice |
Pitfalls
- Using a standard formula and standard keratometry after myopic laser surgery [S4].
- Using SRK II, which performed worst in short eyes and in children [S1] [S6].
- Assuming optical biometry always works in dense cataract [S5].
- Never auditing results or optimising lens constants [S9].
- Aligning toric IOLs without accurate marking [S3].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2018 | Meta-analysis of 10 observational studies |
| [S2] | 2019 | Narrative literature review |
| [S3] | 2019 | RCT, 132 eyes |
| [S4] | 2021 | AAO Ophthalmic Technology Assessment, 11 level III studies |
| [S5] | 2022 | Review of 27 studies |
| [S6] | 2023 | Bayesian network meta-analysis, 13 studies |
| [S7] | 2023 | Systematic review of 29 studies |
| [S8] | 2024 | Network meta-analysis, 10 studies |
| [S9] | 2024 | Narrative review, 121 articles |
| [S10] | 2024 | Literature review |
| [S11] | 2025 | Narrative review |
- Nearly all formula evidence is retrospective and observational; [S4] rated all its studies level III, and [S8] reported no statistically significant differences.
- [S1] predates the newest formulas (Barrett, Kane, PEARL-DGS were not compared).
- [S5] includes an expert opinion that swept-source biometry may be the gold standard; [S10] recommends ultrasound for resource-limited missions. The two fit different settings.
- Not covered by these sources: contact versus immersion ultrasound accuracy, A-constant values, target refraction for monovision, and second-eye adjustment.
Related articles
- Presbyopia-correcting and EDOF intraocular lenses
- Phacoemulsification: outcomes and techniques
- Laser refractive surgery: LASIK, SMILE and PRK
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Wang Q, Jiang W, Lin T, Wu X, Lin H, Chen W Meta-analysis of accuracy of intraocular lens power calculation formulas in short eyes. Clinical & experimental ophthalmology. (2018). PubMed 28887901 · doi:10.1111/ceo.13058
- [S2] Moshirfar M, Buckner B, Ronquillo YC, Hofstedt D Biometry in cataract surgery: a review of the current literature. Current opinion in ophthalmology. (2019). PubMed 30394990 · doi:10.1097/icu.0000000000000536
- [S3] Kim EC, Hwang KY, Lim SA, Yi R, Joo CK Accuracy of toric intraocular lens implantation using automated vs manual marking. BMC ophthalmology. (2019). PubMed 31376834 · doi:10.1186/s12886-019-1175-1
- [S4] Pantanelli SM, Lin CC, Al-Mohtaseb Z, Rose-Nussbaumer JR, Santhiago MR, Steigleman WA, et al. Intraocular Lens Power Calculation in Eyes with Previous Excimer Laser Surgery for Myopia: A Report by the American Academy of Ophthalmology. Ophthalmology. (2021). PubMed 33500124 · doi:10.1016/j.ophtha.2020.10.031
- [S5] Tañá-Rivero P, Tañá-Sanz S, Pastor-Pascual F, Ruiz-Mesa R, Montés-Micó R Axial length measurement failure rates using optical biometry based on swept-source OCT in cataractous eyes. Expert review of medical devices. (2022). PubMed 36062739 · doi:10.1080/17434440.2022.2118047
- [S6] Hong Y, Sun Y, Xiao B, Ainiwaer M, Ji Y A Bayesian network meta-analysis on comparisons of intraocular lens power calculation methods for paediatric cataract eyes. Eye (London, England). (2023). PubMed 37019996 · doi:10.1038/s41433-023-02510-2
- [S7] Stopyra W, Langenbucher A, Grzybowski A Intraocular Lens Power Calculation Formulas-A Systematic Review. Ophthalmology and therapy. (2023). PubMed 37698825 · doi:10.1007/s40123-023-00799-6
- [S8] Ma Y, Xiong R, Liu Z, Young CA, Wu Y, Zheng D, et al. Network Meta-analysis of Intraocular Lens Power Calculation Formula Accuracy in 1016 Eyes With Long Axial Length. American journal of ophthalmology. (2024). PubMed 37726043 · doi:10.1016/j.ajo.2023.09.009
- [S9] Gupta V, Pal H, Sawhney S, Aggarwal A, Vanathi M, Luthra G Optimization of biometry for best refractive outcome in cataract surgery. Indian journal of ophthalmology. (2024). PubMed 38131567 · doi:10.4103/ijo.ijo_1219_23
- [S10] Urbinati F, Jiménez-Siles L, Rocha-de-Lossada C, Valvecchia G, Barraquer-Compte E, Fernández J Humanitarian missions and visual outcomes in cataract surgery: A literature review. Archivos de la Sociedad Espanola de Oftalmologia. (2024). PubMed 38309656 · doi:10.1016/j.oftale.2024.01.008
- [S11] Ma JX, Wang L, Koch DD Intraocular lens power calculation in challenging cases. Saudi journal of ophthalmology : official journal of the Saudi Ophthalmological Society. (2025). PubMed 41367836 · doi:10.4103/sjopt.sjopt_15_24