Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Vitamin A deficiency and xerophthalmia
Vitamin A deficiency (VAD) affects an estimated 190 million children under five in low- and middle-income countries and is associated with ocular impairment, poor growth, more infection and death [S9] [S12]. Vitamin A supplementation (VAS) in children aged 6 to 59 months reduces all-cause mortality by 12% (high-certainty evidence) [S9].
Key points - VAS reduced night blindness (RR 0.32) and Bitot's spots (RR 0.42) in children aged 6 months to 5 years (moderate-certainty evidence) [S9]. - In children with measles, two doses of vitamin A on consecutive days reduced mortality in those under two years [S1] [S2]; no trial has measured whether vitamin A prevents measles blindness [S4]. - Blood tests for VAD have low sensitivity (0% to 54%), so a normal result does not exclude deficiency [S12]. - Fortifying staple foods with vitamin A alone may make little or no difference to serum retinol; multi-micronutrient fortification probably reduces subclinical deficiency [S6]. - Clinical and subclinical VAD remained a public health problem in Ethiopia despite falling night blindness [S7].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: signs that need urgent action
- In a child: night blindness or Bitot's spots, the clinical signs of VAD measured in trials and surveys [S7] [S9].
- In a child: measles, especially under two years; VAD is a risk factor for severe measles, and low vitamin A raises the risk of blindness [S1] [S4].
- In a child: severe acute malnutrition (SAM) with signs of VAD, measles or severe diarrhoea; these children need the high-dose regimen [S3].
- In a population: night blindness above 1% or Bitot's spots above 0.5% in preschool children, the WHO thresholds for a public health problem cited in [S7].
- In a programme: unknown coverage. Annual two-dose VAS coverage was reported in only four of 18 studies [S8].
Recognise it: who is at risk
- Children under five in low- and middle-income countries [S9].
- Young children, women of reproductive age and pregnant women [S6].
- Children with measles, diarrhoea or SAM [S1] [S3].
- In Ethiopian preschool children night blindness fell from 4.2% (1990 to 2004) to 0.8% (2005 to 2019), but Bitot's spots stayed at 1.8% and subclinical VAD at 28.3% [S7].
Confirm it
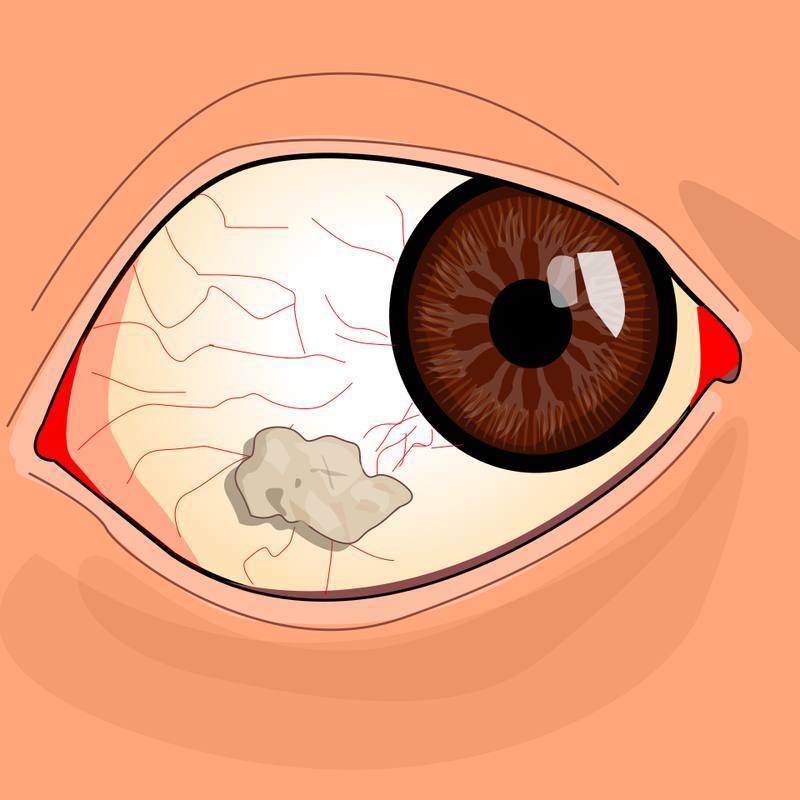
- Clinically: ask about night blindness and look for Bitot's spots [S7] [S9].
- Biochemically: one review defined VAD as clinical ocular signs and/or serum retinol <0.70 μmol/L [S11].
- Test accuracy is poor: serum retinol sensitivity against isotope dilution was 10% to 13%, and retinol-binding protein 45% to 50% (low or very low certainty) [S12]. A normal result therefore does not exclude VAD [S12].
Manage it: what to do at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / community)
- Give routine VAS to children aged 6 to 59 months as WHO recommends [S9]. Vomiting within 48 hours is more common after a dose (RR 1.97) [S9].
- Mortality benefit was not modified by dosing frequency, total dose or duration within the ranges studied [S5].
- Measles: WHO recommends an oral dose of 200,000 IU (100,000 IU in infants) each day for two days in areas where VAD may be present, as reported in [S1]. A single dose was not associated with lower mortality [S1].
- Support measles vaccination, which was 85% effective in preventing measles disease when given before one year of age [S2].
- Promote foods rich in preformed vitamin A and provitamin A carotenoids; some food-based interventions improved vitamin A status [S11].
Tier B (general eye clinic or district hospital)
- Examine children with night blindness, Bitot's spots or measles for eye involvement and ensure vitamin A has been given [S1] [S7].
- SAM: a systematic review recommends a low-dose regimen for children with SAM, except in those with measles, severe diarrhoea (shigellosis) or any sign of VAD, who should receive high-dose vitamin A [S3]. Follow WHO and local formularies for exact doses.
Tier C (specialist centre and planners)
- Measure coverage with cluster surveys that follow the 2018 WHO Vaccination Coverage Cluster Surveys manual until administrative systems can measure routine two-dose coverage [S8].
- Combine supplementation with multi-micronutrient fortification and food-based approaches [S6] [S11].
- Reassess cost-effectiveness locally: a 2022 simulation for Nigeria, Kenya and Burkina Faso found VAS may be less cost-effective than previously estimated ($220 to $860 per DALY) [S10].
Refer when
| Situation | Urgency |
|---|---|
| Child with corneal clouding, ulceration or softening, or a red painful eye with measles or malnutrition | Immediate, same-day, to an eye service; give vitamin A first if available [EIC expert opinion] |
| Child with Bitot's spots or night blindness | Urgent, for eye examination and nutrition care; timing per your local service or specialist advice |
| Child with SAM | Medical emergency: nutrition or paediatric service; follow your national protocol [EIC expert opinion] |
Pitfalls
- Relying on a normal serum retinol or RBP result [S12].
- Giving a single dose in measles; benefit was seen with two doses [S1] [S2].
- Assuming vitamin A-only fortification is enough [S6].
- Giving high-dose VAS routinely to adequately nourished children outside programmes; adverse respiratory, diarrhoeal and growth outcomes were reported [S3].
- Reporting administrative coverage without verifying it [S8].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2005 | Cochrane systematic review and meta-analysis (measles treatment) |
| [S2] | 2010 | Systematic review and meta-analysis (measles vaccine and vitamin A) |
| [S3] | 2013 | Systematic review, RCTs and observational studies (SAM) |
| [S4] | 2016 | Cochrane systematic review, 2 RCTs (measles blindness) |
| [S5] | 2017 | Meta-analysis and meta-regression of 17 RCTs |
| [S6] | 2019 | Cochrane systematic review, 10 RCTs (fortification) |
| [S7] | 2020 | Systematic review and meta-analysis, Ethiopia |
| [S8] | 2021 | Systematic review of coverage methods, 18 studies |
| [S9] | 2022 | Cochrane systematic review, 47 studies, about 1.2 million children |
| [S10] | 2022 | Cost-effectiveness microsimulation |
| [S11] | 2023 | Systematic review, 24 studies (food-based approaches) |
| [S12] | 2025 | Cochrane diagnostic accuracy review, 40 studies |
- The prevention of blindness by vitamin A in measles is untested in trials; neither included trial reported ocular outcomes [S4].
- The measles mortality evidence is from 2005 and 2010 reviews [S1] [S2].
- The SAM review found only one study that replicated the WHO protocol, and indirectness was a critical limitation [S3].
- None of the biomarker studies was designed as a diagnostic accuracy study [S12].
- [S10] is a modelling study and conflicts with the long-held view that VAS is highly cost-effective.
- Not covered by these sources: the full xerophthalmia grading (conjunctival xerosis, corneal xerosis, keratomalacia), treatment doses for xerophthalmia itself, and dosing in pregnancy.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Huiming Y, Chaomin W, Meng M Vitamin A for treating measles in children. The Cochrane database of systematic reviews. (2005). PubMed 16235283 · doi:10.1002/14651858.cd001479.pub3
- [S2] Sudfeld CR, Navar AM, Halsey NA Effectiveness of measles vaccination and vitamin A treatment. International journal of epidemiology. (2010). PubMed 20348126 · doi:10.1093/ije/dyq021
- [S3] Iannotti LL, Trehan I, Manary MJ Review of the safety and efficacy of vitamin A supplementation in the treatment of children with severe acute malnutrition. Nutrition journal. (2013). PubMed 24028603 · doi:10.1186/1475-2891-12-125
- [S4] Bello S, Meremikwu MM, Ejemot-Nwadiaro RI, Oduwole O Routine vitamin A supplementation for the prevention of blindness due to measles infection in children. The Cochrane database of systematic reviews. (2016). PubMed 27580345 · doi:10.1002/14651858.cd007719.pub4
- [S5] Kranz S, Pimpin L, Fawzi W, Duggan C, Webb P, Mozaffarian D Mortality Benefits of Vitamin A Are Not Affected by Varying Frequency, Total Dose, or Duration of Supplementation. Food and nutrition bulletin. (2017). PubMed 28513263 · doi:10.1177/0379572117696663
- [S6] Hombali AS, Solon JA, Venkatesh BT, Nair NS, Peña-Rosas JP Fortification of staple foods with vitamin A for vitamin A deficiency. The Cochrane database of systematic reviews. (2019). PubMed 31074495 · doi:10.1002/14651858.cd010068.pub2
- [S7] Sahile Z, Yilma D, Tezera R, Bezu T, Haileselassie W, Seifu B, et al. Prevalence of Vitamin A Deficiency among Preschool Children in Ethiopia: A Systematic Review and Meta-Analysis. BioMed research international. (2020). PubMed 32258145 · doi:10.1155/2020/8032894
- [S8] Miglietta A, Imohe A, Hasman A Methodologies to measure the coverage of vitamin A supplementation: a systematic review. Journal of nutritional science. (2021). PubMed 34527226 · doi:10.1017/jns.2021.65
- [S9] Imdad A, Mayo-Wilson E, Haykal MR, Regan A, Sidhu J, Smith A, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. The Cochrane database of systematic reviews. (2022). PubMed 35294044 · doi:10.1002/14651858.cd008524.pub4
- [S10] Kannan A, Tsoi D, Xie Y, Horst C, Collins J, Flaxman A Cost-effectiveness of Vitamin A supplementation among children in three sub-Saharan African countries: An individual-based simulation model using estimates from Global Burden of Disease 2019. PloS one. (2022). PubMed 35390077 · doi:10.1371/journal.pone.0266495
- [S11] Nankumbi J, Grant F, Sibeko L, Mercado E, O'Neil K, Cordeiro LS Effects of Food-Based Approaches on Vitamin A Status of Women and Children: A Systematic Review. Advances in nutrition (Bethesda, Md.). (2023). PubMed 37634852 · doi:10.1016/j.advnut.2023.08.009
- [S12] Gannon BM, Huey SL, Mehta NH, Shrestha N, Lopez-Perez L, Martinez RX, et al. Selected laboratory-based biomarkers for assessing vitamin A deficiency in at-risk individuals. The Cochrane database of systematic reviews. (2025). PubMed 40433851 · doi:10.1002/14651858.cd013742.pub2