Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Uveitic Macular Oedema
Uveitic macular oedema (UMO) is the most common cause of visual loss in uveitis [S3]. Regional corticosteroids have the strongest comparative evidence [S2] [S4] [S8], but raise intraocular pressure (IOP) [S2] [S8]. With enough time and treatment nearly all UMO resolves, although relapse is common [S6].
Key points - In comparative studies, corticosteroids (all forms) were consistently as effective as or more effective than active comparators [S4]. - Intravitreal triamcinolone and the dexamethasone implant reduced macular thickness more than periocular triamcinolone (POINT RCT) [S2]. - For persistent or recurrent UMO, the dexamethasone implant outperformed intravitreal methotrexate and ranibizumab at 12 and 24 weeks (MERIT RCT) [S8] [S10]. - About half of eyes on methotrexate or mycophenolate still had UMO at 12 months [S7]. - Resolved UMO relapsed in 43% of eyes within 7 years, so long-term follow-up is needed [S6].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Vision falling with new or relapsing UMO. Eyes that developed UMO during a year lost a mean of 8.65 letters [S6].
- IOP rise after steroid injection. With the dexamethasone implant, IOP of 24 mmHg or more occurred in 32% and of 30 mmHg or more in 10% by 24 weeks [S10]; intravitreal routes carried a higher risk of IOP of 24 mmHg or more than periocular injection [S2].
- Persistent UMO despite systemic therapy. About half of eyes had persistent UMO at 12 months on antimetabolites [S7].
- Epiretinal membrane on OCT was associated with a lower likelihood of resolution [S6].
Recognise it
- UMO is one of the most common sight-threatening complications of uveitis [S1] [S3].
- The aim of treatment is to restore macular architecture quickly, to prevent irreversible photoreceptor damage [S3].
Confirm it
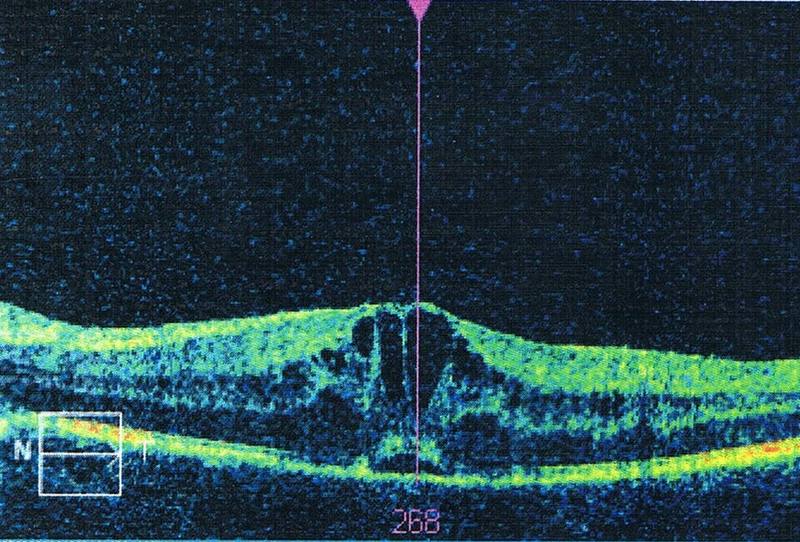
- OCT is the standard measure in trials: central subfield or central macular thickness, assessed by masked readers [S2] [S8].
- MUST defined UMO as central macular thickness of 240 μm or more on time-domain OCT or its equivalent [S6].
- Where OCT is not available, these sources do not describe an alternative diagnostic method.
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Anyone with uveitis and blurred central vision needs eye-clinic assessment; UMO is the leading cause of visual loss in uveitis [S3]. Timing is in the table below.
Tier B (general eye clinic)
- Control the uveitis. Acute exacerbations are typically managed with corticosteroids given topically, locally or systemically; steroid-sparing agents are used for severe or recalcitrant disease [S3].
- Regional steroid choice. In POINT, macular thickness fell at 8 weeks by 23% with periocular triamcinolone, 39% with intravitreal triamcinolone and 46% with the dexamethasone implant [S2]. Both intravitreal options were superior to periocular injection and gave about 5 letters more vision gain at 8 weeks [S2].
- Intravitreal triamcinolone dose. In a small Brazilian RCT (32 eyes), 4 mg gave a greater reduction in central retinal thickness than 2 mg (doses as reported in [S11]); recurrence was 25% vs 50% (not significant), with transient IOP spikes at 7 days in both groups [S11].
- Check IOP after every injection [S2] [S10]. Other dosing is not covered by these abstracts: follow local formularies.
- Oral acetazolamide is a low-cost option with weak evidence: a meta-analysis of 7 studies (187 participants) found visual improvement in a pooled 53%, but the difference from placebo was not significant [S12]. An earlier systematic review judged carbonic anhydrase inhibitors not effective [S4].
Tier C (specialist centre)
- Persistent or recurrent UMO (MERIT, 194 participants). At 12 weeks, macular thickness fell 35% with the dexamethasone implant, 11% with intravitreal methotrexate and 22% with ranibizumab; only the implant improved visual acuity significantly (4.86 letters) [S8]. At 24 weeks the implant remained more effective; methotrexate- and ranibizumab-assigned eyes often needed other treatment [S10].
- Suprachoroidal triamcinolone (CLS-TA). In a phase 3 RCT (160 patients), 47% gained 15 or more letters at week 24 vs 16% with sham; elevated IOP occurred in 11.5% vs 15.6% [S5].
- Non-steroidal intravitreal agents. A meta-analysis of 17 mostly small studies (258 eyes) found improvement in thickness and acuity with anti-VEGF, infliximab, methotrexate and diclofenac [S9]. In an Iranian RCT (60 eyes), improvement in visual acuity at 6 months was 96% with triamcinolone 4 mg and 83% with bevacizumab 1.25 mg (doses as reported in [S1]), not a significant difference [S1]. Anti-VEGF improvement was mostly less than with local steroid injection [S4].
- Systemic antimetabolites. In FAST, methotrexate and mycophenolate gave similar reductions in macular thickness at 6 and 12 months [S7].
- Anti-TNF agents. A Cochrane review found no randomised trials reporting UMO outcomes, so there is insufficient evidence for a UMO-specific effect [S3].
Refer when
| Situation | Urgency |
|---|---|
| Uveitis with new loss of central vision | Emergency referral to an eye clinic with OCT [S3] [EIC expert opinion] |
| IOP rise after steroid injection that topical drops do not control | Urgent to a glaucoma-capable service; timing per your local service or specialist advice [S10] |
| UMO persisting after regional steroid, or steroid-induced IOP rise limiting further steroid | Routine to a uveitis specialist; timing per your local service or specialist advice [S8] [S10] |
Pitfalls
- Choosing periocular injection when intravitreal options are available; periocular triamcinolone was less effective [S2].
- Expecting systemic antimetabolites alone to clear UMO [S7].
- Stopping follow-up after resolution; relapse is common [S6].
- Treating anti-VEGF as equal to steroid for UMO [S4] [S8].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | RCT, 60 eyes, Iran |
| [S2] | 2019 | Multicentre RCT (POINT) |
| [S3] | 2018 | Cochrane review, no eligible trials |
| [S4] | 2019 | Systematic review, 31 studies |
| [S5] | 2020 | Phase 3 RCT (PEACHTREE), sham controlled |
| [S6] | 2021 | 7-year follow-up of a trial cohort (MUST) |
| [S7] | 2022 | Subanalysis of an RCT (FAST, India-led) |
| [S8] | 2023 | Multicentre RCT (MERIT), 12 weeks |
| [S9] | 2024 | Meta-analysis, 17 studies |
| [S10] | 2025 | MERIT 24-week outcomes |
| [S11] | 2025 | Small RCT, 32 eyes, Brazil |
| [S12] | 2026 | Meta-analysis, 7 studies, Indonesian authors |
- Conflict: the carbonic anhydrase inhibitor evidence is mixed; one review found no benefit [S4] and a later meta-analysis found pooled improvement that did not differ significantly from placebo [S12].
- The non-steroidal meta-analysis compared last follow-up with baseline, not with a control group [S9].
- MERIT reports proprietary or commercial disclosures in the full papers [S8] [S10]; details are not in the abstracts.
- Not covered by these sources: UMO in infectious uveitis, topical NSAIDs, fluocinolone implants for UMO specifically, cost and injection access in low-resource settings, and diagnosis without OCT.
Related articles
- Biologics and Immunosuppression for Non-infectious Uveitis
- OCT interpretation: macula and retinal nerve fibre layer
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Rahimi M, Shahrzad SS, Banifatemi M Comparison of intravitreal injection of bevacizumab and triamcinolone acetonide in the treatment of uveitic macular edema. Iranian journal of immunology : IJI. (2012). PubMed 22735801 · doi:10.22034/iji.2012.16865
- [S2] Thorne JE, Sugar EA, Holbrook JT, Burke AE, Altaweel MM, Vitale AT, et al. Periocular Triamcinolone vs. Intravitreal Triamcinolone vs. Intravitreal Dexamethasone Implant for the Treatment of Uveitic Macular Edema: The PeriOcular vs. INTravitreal corticosteroids for uveitic macular edema (POINT) Trial. Ophthalmology. (2019). PubMed 30269924 · doi:10.1016/j.ophtha.2018.08.021
- [S3] Barry RJ, Tallouzi MO, Bucknall N, Mathers JM, Murray PI, Calvert MJ, et al. Anti-tumour necrosis factor biological therapies for the treatment of uveitic macular oedema (UMO) for non-infectious uveitis. The Cochrane database of systematic reviews. (2018). PubMed 30562409 · doi:10.1002/14651858.cd012577.pub2
- [S4] Tallouzi MO, Moore DJ, Barry RJ, Calvert M, Mathers J, Murray PI, et al. The Effectiveness of Pharmacological Agents for the Treatment of Uveitic Macular Edema (UMO): A Systematic Review. Ocular immunology and inflammation. (2019). PubMed 30811272 · doi:10.1080/09273948.2019.1569243
- [S5] Yeh S, Khurana RN, Shah M, Henry CR, Wang RC, Kissner JM, et al. Efficacy and Safety of Suprachoroidal CLS-TA for Macular Edema Secondary to Noninfectious Uveitis: Phase 3 Randomized Trial. Ophthalmology. (2020). PubMed 32173113 · doi:10.1016/j.ophtha.2020.01.006
- [S6] Tomkins-Netzer O, Lightman SL, Burke AE, Sugar EA, Lim LL, Jaffe GJ, et al. Seven-Year Outcomes of Uveitic Macular Edema: The Multicenter Uveitis Steroid Treatment Trial and Follow-up Study Results. Ophthalmology. (2021). PubMed 32918964 · doi:10.1016/j.ophtha.2020.08.035
- [S7] Tsui E, Rathinam SR, Gonzales JA, Thundikandy R, Kanakath A, Balamurugan S, et al. Outcomes of Uveitic Macular Edema in the First-line Antimetabolites as Steroid-Sparing Treatment Uveitis Trial. Ophthalmology. (2022). PubMed 35143800 · doi:10.1016/j.ophtha.2022.02.002
- [S8] Multicenter Uveitis Steroid Treatment Trial (MUST) Research Group, Writing Committee:, Acharya NR, Vitale AT, Sugar EA, Holbrook JT, Burke AE, et al. Intravitreal Therapy for Uveitic Macular Edema-Ranibizumab versus Methotrexate versus the Dexamethasone Implant: The MERIT Trial Results. Ophthalmology. (2023). PubMed 37318415 · doi:10.1016/j.ophtha.2023.04.011
- [S9] Kianersi F, Rezaeian-Ramsheh A, Rahimi A, Akhlaghi M, Dehghani A, Farajzadegan Z, et al. Non-steroidal intravitreal injection for noninfectious uveitic cystoid macular edema: Systematic review and meta-analysis. European journal of ophthalmology. (2024). PubMed 37933173 · doi:10.1177/11206721231212777
- [S10] Multicenter Uveitis Steroid Treatment Trial (MUST) Research Group, Gonzales J, Acharya NR, Sugar EA, Burke AE, Vitale AT, et al. Macular Edema Ranibizumab versus Intravitreal Anti-inflammatory Therapy Trial: 24-Week Outcomes of Uveitic Macular Edema Re-treatment. Ophthalmology. (2025). PubMed 39612949 · doi:10.1016/j.ophtha.2024.11.021
- [S11] Eduardo de Souza C, Zanetti Patricio de Macedo B, Viana de Sousa M, Naomi Morimoto L, Lima LH, Muccioli C Treatment of Non-Infectious Uveitis Macular Edema Using Two Doses of Triamcinolone Acetonide: Comparative Study. Ocular immunology and inflammation. (2025). PubMed 40478537 · doi:10.1080/09273948.2025.2504580
- [S12] Excelinda T, Putera I, Ridwan AS, La Distia Nora R CARBONIC ANHYDRASE INHIBITORS FOR MANAGING UVEITIC MACULAR EDEMA: A Systematic Review and Meta-Analysis. Retina (Philadelphia, Pa.). (2026). PubMed 40865073 · doi:10.1097/iae.0000000000004646