Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Topical and periocular corticosteroids: benefits and risks
Corticosteroids remain the mainstay of treatment for many inflammatory conditions of the ocular surface, anterior and posterior segment, given as drops, periocular or intravitreal injections, or implants [S8]. Their main local risks are raised intraocular pressure (IOP) and cataract [S8], and in infectious keratitis they can suppress the host response needed to clear infection [S10].
Key points - Steroid-induced IOP elevation and cataract are the most significant local risks of topical and systemic corticosteroids [S8]; injected and implanted routes may exacerbate them [S8]. - Topical steroids are safe as an adjunct in bacterial keratitis with broad-spectrum antibiotics and in herpetic keratitis with antivirals, but observational studies found harm in fungal and Acanthamoeba keratitis when started before anti-amoebic therapy [S10]. - In dry eye, topical steroids probably give small to moderate symptom relief beyond lubricants, but may increase IOP elevation (RR 5.96) [S9]. - Loteprednol etabonate was designed to have less effect on IOP than prednisolone acetate or dexamethasone [S1]. - In most cases of uveitis, corticosteroids are not appropriate as long-term therapy [S7].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Red eye with a corneal infiltrate or ulcer of unknown cause: steroids may hinder clearance of infection, and observational studies show harm in fungal and Acanthamoeba keratitis [S10].
- Raised IOP during steroid treatment, especially in known steroid responders, glaucoma or pre-existing optic nerve damage [S5] [S8].
- Long-term or repeated steroid courses without IOP and lens monitoring [S7] [S8].
- Systemic effects with systemic steroids, such as osteonecrosis and adrenal insufficiency [S7].
Recognise it: benefits and harms by route
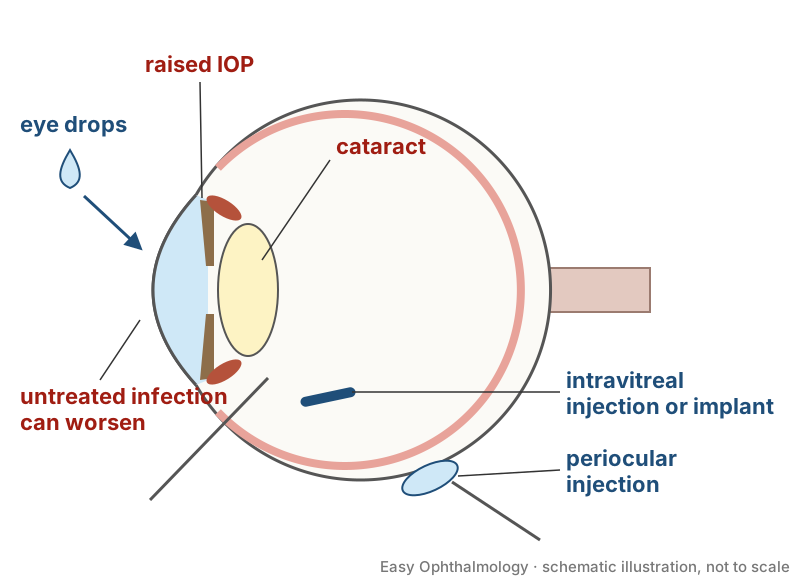
- Topical drops are the route of choice for ocular surface and anterior segment disease [S8].
- Periocular, intravitreal and suprachoroidal injections can be effective for posterior segment disease [S8].
- Raised IOP after cataract surgery. Early postoperative IOP rise is frequent; risk factors include residual viscoelastic, glaucoma, pseudoexfoliation, axial length over 25 mm, tamsulosin and topical steroids in steroid responders [S5]. Stopping the corticosteroid usually returns IOP to normal in steroid responders [S5].
- Older steroids such as dexamethasone and prednisolone acetate are often associated with clinically significant IOP rises of 10 mmHg or more, as reported in [S1].
Confirm it: monitoring
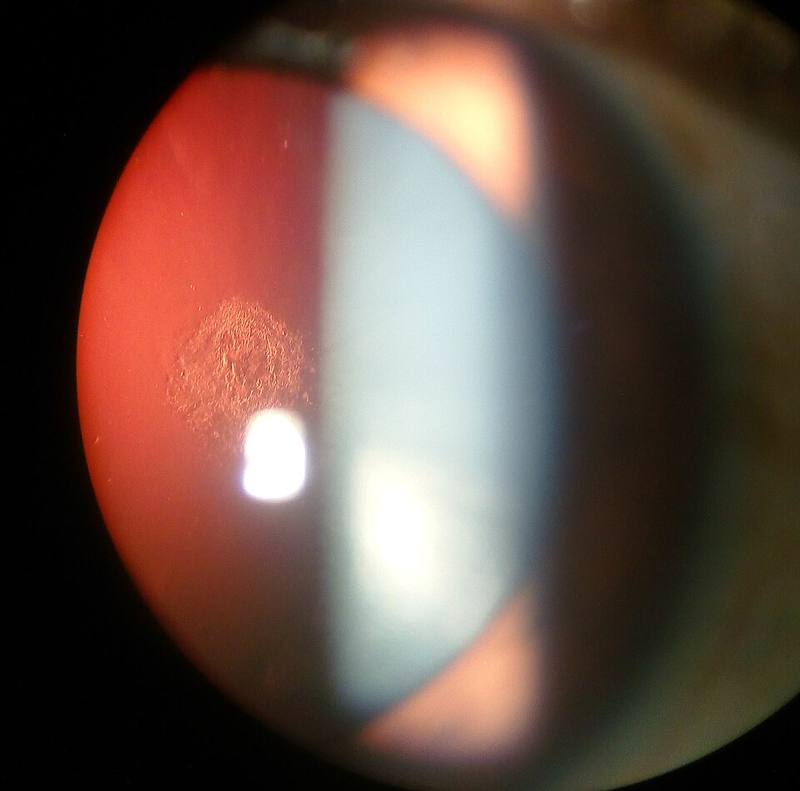
- IOP elevation is the most significant local risk, so check IOP during treatment where a tonometer is available [S8].
- Examine the lens for cataract on longer courses [S8].
- Before starting steroids for keratitis, consider the likely organism: their safety depends largely on the efficacy of the antimicrobial against that organism [S10].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Avoid starting topical steroid drops for an undiagnosed red eye: steroids reduce the host immune response and can worsen untreated infection [S10].
- Ask about steroid drops in any patient with a painful red eye or new loss of vision, and refer for IOP measurement [S8].
- Dosing is not covered here: follow your local formulary.
Tier B (general eye clinic)
- After cataract surgery. A meta-analysis of 6 RCTs (883 patients) found difluprednate cleared anterior chamber cells faster than prednisolone acetate after small incision cataract surgery and gave clearer corneas after phacoemulsification; there was no difference at 1 month and no significant difference in ocular hypertension (OR 1.23) [S6]. Certainty was low to moderate [S6].
- Dry eye. A Cochrane review of 22 RCTs (4169 participants) found small to moderate symptom benefit over lubricants; trials lasted mostly weeks, so long-term effects on IOP and cataract are uncertain [S9].
- Paediatric blepharokeratoconjunctivitis. Only one small RCT (137 children aged 0 to 6 years) was found, with very low certainty evidence and no important differences between loteprednol/tobramycin, loteprednol, tobramycin and placebo [S3].
- Bacterial keratitis. Adjunctive steroids with broad-spectrum antibiotics are safe; benefit has not been shown conclusively, although more advanced ulcers may do better [S10]. No RCTs have assessed steroids in fungal or Acanthamoeba keratitis [S10].
- IOP spikes in steroid responders. Stop or reduce the steroid; one review suggests topical IOP-lowering combinations in high-risk patients [S5].
Tier C (specialist centre)
- Uveitic macular oedema. In the POINT RCT, intravitreal triamcinolone and the dexamethasone implant reduced central subfield thickness more than periocular triamcinolone (39% and 46% vs 23% at 8 weeks), with modestly higher risk of IOP of 24 mmHg or more [S4].
- Chronic non-infectious posterior, intermediate or panuveitis. A fluocinolone acetonide implant probably reduced recurrence (RR 0.29) but increased the need for cataract surgery (RR 2.98) and IOP-lowering surgery (RR 7.48) over two years; the review could not conclude that implants are superior to systemic therapy [S2].
- Plan steroid-sparing long-term therapy in uveitis [S7].
Refer when
| Situation | Urgency |
|---|---|
| Patient on steroid drops with a painful red eye, worsening corneal infiltrate or reduced vision | Same-day to an eye unit [S10] [G1] |
| Raised IOP on steroid treatment, or a known glaucoma patient needing steroids | Urgent for specialist review [S5]; timing per your local service or specialist advice |
| Steroid drops continued for months without monitoring | Routine, for IOP and lens check; timing per your local service or specialist advice |
Pitfalls
- Prescribing steroid drops for a red eye without first excluding infection, especially fungal or Acanthamoeba keratitis [S10].
- Forgetting that intravitreal and implant routes carry higher IOP and cataract risk [S2] [S4] [S8].
- Assuming short dry eye trials prove long-term safety [S9].
- Relying on corticosteroids as long-term uveitis therapy [S7].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | Narrative review |
| [S2] | 2016 | Cochrane systematic review, 2 RCTs |
| [S3] | 2017 | Cochrane systematic review, 1 RCT |
| [S4] | 2019 | Multicentre RCT (POINT) |
| [S5] | 2019 | Narrative review |
| [S6] | 2019 | Meta-analysis of 6 RCTs |
| [S7] | 2020 | Narrative review |
| [S8] | 2021 | Narrative review |
| [S9] | 2022 | Cochrane systematic review, 22 RCTs |
| [S10] | 2023 | Narrative review |
- In the dry eye review, nearly half the trials were at high risk of bias from selective reporting, and 8 were sponsored exclusively by industry [S9].
- The implant review included two studies, both at high risk of performance and detection bias [S2].
- Loteprednol comparisons with difluprednate need confirmatory studies [S1].
- Not covered by these sources: steroid doses and tapering, steroids in pregnancy and children beyond BKC, combination antibiotic-steroid drops in primary care, and steroid misuse from over-the-counter sale.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Amon M, Busin M Loteprednol etabonate ophthalmic suspension 0.5 %: efficacy and safety for postoperative anti-inflammatory use. International ophthalmology. (2012). PubMed 22707339 · doi:10.1007/s10792-012-9589-2
- [S2] Brady CJ, Villanti AC, Law HA, Rahimy E, Reddy R, Sieving PC, et al. Corticosteroid implants for chronic non-infectious uveitis. The Cochrane database of systematic reviews. (2016). PubMed 26866343 · doi:10.1002/14651858.cd010469.pub2
- [S3] O'Gallagher M, Bunce C, Hingorani M, Larkin F, Tuft S, Dahlmann-Noor A Topical treatments for blepharokeratoconjunctivitis in children. The Cochrane database of systematic reviews. (2017). PubMed 28170093 · doi:10.1002/14651858.cd011965.pub2
- [S4] Thorne JE, Sugar EA, Holbrook JT, Burke AE, Altaweel MM, Vitale AT, et al. Periocular Triamcinolone vs. Intravitreal Triamcinolone vs. Intravitreal Dexamethasone Implant for the Treatment of Uveitic Macular Edema: The PeriOcular vs. INTravitreal corticosteroids for uveitic macular edema (POINT) Trial. Ophthalmology. (2019). PubMed 30269924 · doi:10.1016/j.ophtha.2018.08.021
- [S5] Grzybowski A, Kanclerz P Early postoperative intraocular pressure elevation following cataract surgery. Current opinion in ophthalmology. (2019). PubMed 30489361 · doi:10.1097/icu.0000000000000545
- [S6] KhalafAllah MT, Basiony A, Salama A Difluprednate versus Prednisolone Acetate after Cataract Surgery: a Systematic Review and Meta-Analysis. BMJ open. (2019). PubMed 31678934 · doi:10.1136/bmjopen-2018-026752
- [S7] Valdes LM, Sobrin L Uveitis Therapy: The Corticosteroid Options. Drugs. (2020). PubMed 32350761 · doi:10.1007/s40265-020-01314-y
- [S8] Gaballa SA, Kompella UB, Elgarhy O, Alqahtani AM, Pierscionek B, Alany RG, et al. Corticosteroids in ophthalmology: drug delivery innovations, pharmacology, clinical applications, and future perspectives. Drug delivery and translational research. (2021). PubMed 32901367 · doi:10.1007/s13346-020-00843-z
- [S9] Liu SH, Saldanha IJ, Abraham AG, Rittiphairoj T, Hauswirth S, Gregory D, et al. Topical corticosteroids for dry eye. The Cochrane database of systematic reviews. (2022). PubMed 36269562 · doi:10.1002/14651858.cd015070.pub2
- [S10] Keenan JD Steroids in the Management of Infectious Keratitis. Cornea. (2023). PubMed 38112645 · doi:10.1097/ico.0000000000003340
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 5.12 Keratitis, Microbial, Bacterial (2026). https://www.eyes.nhs.scot/eyecare-guidelines/section-5-corneal/512-keratitis-microbial-bacterial/