Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
NMOSD and MOG Antibody-Associated Disease
Neuromyelitis optica spectrum disorder (NMOSD) is a severe autoimmune disease of the central nervous system, often misdiagnosed as multiple sclerosis; aquaporin-4 antibodies (AQP4-IgG) confirm the diagnosis and have enabled targeted therapy [S10] [S11]. MOG antibody-associated disease (MOGAD) is a distinct entity with a different course and treatment response [S9]. Optic neuritis is the most common manifestation of NMOSD and can cause rapid, severe and sometimes bilateral loss of vision with frequent sequelae [S11].
Key points - Treat an NMOSD attack as an emergency with intravenous corticosteroids and plasma exchange, without waiting for antibody confirmation [S11]. - Long-term relapse prevention is essential in NMOSD; RCTs show that eculizumab, inebilizumab, satralizumab and rituximab reduce relapses [S1] [S2] [S3] [S4]. - Where biologics are not accessible, conventional immunosuppressants remain alternatives [S10]; rituximab appears more effective than mycophenolate as first-line therapy [S6]. - MOGAD attacks are often very responsive to high-dose intravenous corticosteroids, but relapses occur in more than 40% of adults after 5 years [S9]. - NMOSD is more frequent in Asian and African populations than in European ones, yet data from Africa are scarce [S7].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Severe or bilateral optic neuritis, with a risk of very low long-term acuity in NMOSD [S11].
- Longitudinally extensive, centrally located spinal cord lesions (myelitis), which may lead to tetraplegia [S11].
- Area postrema syndrome: nausea, vomiting and severe hiccups that resist conventional treatment [S11].
- Pregnancy and the postpartum period: NMOSD pregnancy is high risk and attack risk increases after delivery [S11].
- Misdiagnosis as multiple sclerosis [S10].
Recognise it
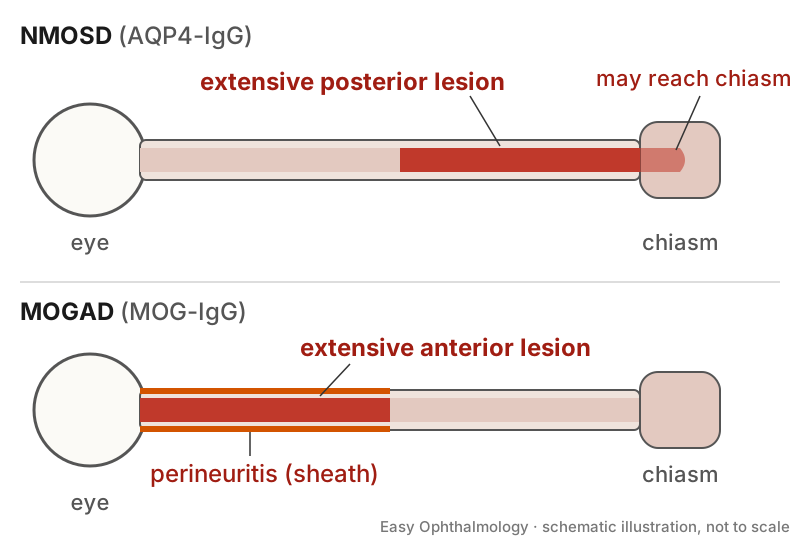
NMOSD - MRI shows extensive optic nerve lesions, mostly in the posterior part of the nerve and sometimes reaching the chiasm [S11]. - At least two thirds of cases are associated with AQP4-IgG [S1]. - In an African systematic review (19 studies, 410 cases in 10 of 54 countries), mean age at diagnosis was 33 years and 75% were female; transverse myelitis followed by optic neuritis were the most frequent presenting symptoms [S7].
MOGAD - MOGAD affects adults and children, more often children [S9]. - Children under 10 often present with acute disseminated encephalomyelitis; older children and adults more often present with unilateral or bilateral optic neuritis or myelitis [S9]. - MRI clues: extensive anterior optic nerve involvement, perineuritis, and spinal cord lesions involving the conus [S9]. - Visual and other sequelae occur much less often than in NMOSD [S9].
Confirm it
- MENACTRIMS (2026, regional consensus for the Middle East and North Africa) endorses the 2015 International Panel criteria and AQP4-IgG testing by cell-based assay [S10].
- Consider multiple sclerosis, MOGAD and acute disseminated encephalomyelitis in the differential [S10].
- MOGAD is confirmed by serum anti-MOG antibodies; if in doubt, confirm in a reference laboratory [S9].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Suspect NMOSD in severe optic neuritis, myelitis or intractable hiccups and vomiting [S11]. Attacks are an emergency: arrange immediate transfer to a centre able to give intravenous corticosteroids and plasma exchange [S11].
- In known NMOSD, do not stop maintenance therapy without specialist advice; prevention of relapses limits disability [S11].
Tier B (general eye clinic)
- Document acuity and fields; involve neurology. Follow-up is multidisciplinary [S11] [S9].
- Start treatment without waiting for antibody results when an NMOSD attack is suspected [S11]; send AQP4-IgG and MOG-IgG [S10] [S9].
- Doses of steroids are not given in these abstracts: follow local protocols.
Tier C (specialist centre)
Acute attacks 1. NMOSD: prompt high-dose intravenous methylprednisolone, with early plasma exchange for severe or steroid-refractory attacks [S10]; the French guideline advises corticosteroids and plasma exchange for attacks [S11]. - Timing evidence conflicts. A meta-analysis of 8 observational studies (228 patients) found plasma exchange reduced EDSS by -1.04 and suggested an optimal start 8 to 23 days after onset; 20.8% had adverse events [S5]. Guidelines favour early use [S10] [S11]. 2. MOGAD: high-dose intravenous corticosteroids followed by an oral taper [S9]. A 2026 meta-analysis (10 publications, 1045 patients) found plasmapheresis associated with improved logMAR acuity (mean difference 1.43) in optic neuritis and an excellent recovery rate of 81%, with adverse effects in 3%; heterogeneity was high and RCTs are needed [S12].
NMOSD relapse prevention (RCT evidence) 3. Eculizumab (PREVENT, 143 AQP4-positive adults): relapses in 3% vs 43% with placebo (hazard ratio 0.06); no significant difference in disability; one death from pulmonary empyema [S1]. Dose as reported in [S1]: 900 mg weekly for 4 doses, then 1200 mg every 2 weeks. Industry-funded. 4. Inebilizumab (N-MOmentum, 230 participants, 25 countries): attacks in 12% vs 39% (hazard ratio 0.272); stopped early for efficacy [S2]. Industry-funded. 5. Satralizumab added to immunosuppressants (83 patients): relapse in 20% vs 43% (hazard ratio 0.38); in AQP4-positive patients 11% vs 43%, in AQP4-negative patients 36% vs 43% (not significant) [S3]. Industry-funded. 6. Rituximab (RIN-1, Japan, 38 AQP4-positive patients): no relapses vs 7 (37%) with placebo over 72 weeks; small trial with mild disease activity [S4]. 7. Choice of agent: monoclonal antibodies (rituximab, inebilizumab, eculizumab, ravulizumab, satralizumab or tocilizumab) according to availability and patient factors; conventional immunosuppressants when biologics are inaccessible [S10]. Azathioprine or mycophenolate are less used first-line but remain possible [S11]. In a meta-analysis of 919 patients, relapse risk was higher with mycophenolate than rituximab (hazard ratio 1.55); azathioprine vs rituximab was not significantly different (1.42) [S6]. 8. Pregnancy: plan after 12 months or more of disease stability and resume treatment early after delivery [S10].
MOGAD relapse prevention 9. Long-term therapy may be proposed, particularly after a relapse, after discussion with a reference centre [S9]. A meta-analysis of mainly retrospective studies found relapse-free proportions of 65% with azathioprine, 73% mycophenolate, 66% rituximab, 79% maintenance IVIG and 93% tocilizumab [S8].
Low-resource note: in Africa, relapses were treated with intravenous methylprednisolone and azathioprine with steroids were the most used maintenance treatments; outcomes were rarely reported [S7].
Refer when
| Situation | Urgency |
|---|---|
| Suspected NMOSD attack (severe optic neuritis, myelitis, area postrema syndrome) | Immediate: treat as an emergency [S11] |
| Suspected MOGAD optic neuritis | Urgent referral, for intravenous steroids [S9] [EIC expert opinion] |
| Poor recovery after steroids | Urgent, for plasma exchange; timing per your local service or specialist advice [S10] [S12] |
| Stable NMOSD or MOGAD on treatment | Routine reference-centre review at least once a year [S9] |
Pitfalls
- Waiting for antibody results before treating an NMOSD attack [S11].
- Labelling NMOSD as multiple sclerosis [S10].
- Assuming satralizumab works equally in AQP4-negative disease; the subgroup difference was not significant [S3].
- Assuming MOGAD is always monophasic: adult relapse risk exceeds 40% at 5 years [S9].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2019 | Phase 3 RCT (PREVENT), 143 patients; industry-funded |
| [S2] | 2019 | Phase 2/3 RCT (N-MOmentum), 230 patients; industry-funded |
| [S3] | 2019 | Phase 3 RCT (SAkuraSky), 83 patients; industry-funded |
| [S4] | 2020 | RCT (RIN-1), 38 patients, Japan; government funded |
| [S5] | 2021 | Meta-analysis of 8 observational studies |
| [S6] | 2021 | Meta-analysis, 919 patients |
| [S7] | 2021 | Systematic review, Africa, mainly retrospective |
| [S8] | 2023 | Meta-analysis, 41 mostly retrospective studies |
| [S9] | 2025 | National guideline (France), MOGAD |
| [S10] | 2026 | Regional consensus guideline (MENACTRIMS) |
| [S11] | 2026 | National guideline (France), NMOSD |
| [S12] | 2026 | Systematic review and meta-analysis, MOGAD |
- Conflict: guidelines advise early plasma exchange [S10] [S11], while an observational meta-analysis reported greater EDSS reduction when started 8 to 23 days after onset [S5]. The abstract does not explain the difference; early use remains guideline advice.
- The four biologic RCTs used placebo comparators and three were industry-funded [S1] [S2] [S3]; there are no head-to-head trials in these sources.
- MOGAD treatment evidence is observational [S8] [S12].
- Not covered by these sources: cost and access to biologics, vaccination and infection screening before immunotherapy, steroid doses, and ravulizumab or tocilizumab trial data.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Pittock SJ, Berthele A, Fujihara K, Kim HJ, Levy M, Palace J, et al. Eculizumab in Aquaporin-4-Positive Neuromyelitis Optica Spectrum Disorder. The New England journal of medicine. (2019). PubMed 31050279 · doi:10.1056/nejmoa1900866
- [S2] Cree BAC, Bennett JL, Kim HJ, Weinshenker BG, Pittock SJ, Wingerchuk DM, et al. Inebilizumab for the treatment of neuromyelitis optica spectrum disorder (N-MOmentum): a double-blind, randomised placebo-controlled phase 2/3 trial. Lancet (London, England). (2019). PubMed 31495497 · doi:10.1016/s0140-6736(19)31817-3
- [S3] Yamamura T, Kleiter I, Fujihara K, Palace J, Greenberg B, Zakrzewska-Pniewska B, et al. Trial of Satralizumab in Neuromyelitis Optica Spectrum Disorder. The New England journal of medicine. (2019). PubMed 31774956 · doi:10.1056/nejmoa1901747
- [S4] Tahara M, Oeda T, Okada K, Kiriyama T, Ochi K, Maruyama H, et al. Safety and efficacy of rituximab in neuromyelitis optica spectrum disorders (RIN-1 study): a multicentre, randomised, double-blind, placebo-controlled trial. The Lancet. Neurology. (2020). PubMed 32199095 · doi:10.1016/s1474-4422(20)30066-1
- [S5] Huang X, Wu J, Xiao Y, Zhang Y Timing of plasma exchange for neuromyelitis optica spectrum disorders: A meta-analysis. Multiple sclerosis and related disorders. (2021). PubMed 33385827 · doi:10.1016/j.msard.2020.102709
- [S6] Giovannelli J, Ciron J, Cohen M, Kim HJ, Kim SH, Stellmann JP, et al. A meta-analysis comparing first-line immunosuppressants in neuromyelitis optica. Annals of clinical and translational neurology. (2021). PubMed 34505407 · doi:10.1002/acn3.51451
- [S7] Musubire AK, Derdelinckx J, Reynders T, Meya DB, Bohjanen PR, Cras P, et al. Neuromyelitis Optica Spectrum Disorders in Africa: A Systematic Review. Neurology(R) neuroimmunology & neuroinflammation. (2021). PubMed 34663674 · doi:10.1212/nxi.0000000000001089
- [S8] Chang X, Zhang J, Li S, Wu P, Wang R, Zhang C, et al. Meta-analysis of the effectiveness of relapse prevention therapy for myelin-oligodendrocyte glycoprotein antibody-associated disease. Multiple sclerosis and related disorders. (2023). PubMed 36905816 · doi:10.1016/j.msard.2023.104571
- [S9] Giorgi L, Marignier R, Pique J, Maurey H, Papeix C, Ciron J, et al. French guidelines for the diagnosis and management of MOG antibody-associated disease. Revue neurologique. (2025). PubMed 40494723 · doi:10.1016/j.neurol.2025.04.012
- [S10] Yamout B, Gouider R, Al-Roughani R, Aljarallah S, Shalaby N, Al-Khabouri J, et al. Consensus Recommendations for the Diagnosis and Treatment of Neuromyelitis Optica Spectrum Disorders (NMOSD): The MENACTRIMS Guidelines. CNS drugs. (2026). PubMed 41591715 · doi:10.1007/s40263-025-01260-x
- [S11] Giorgi L, Marignier R, Pique J, Maurey H, Papeix C, Ciron J, et al. French guidelines for the diagnosis and management of neuromyelitis optica spectrum disorder. Revue neurologique. (2026). PubMed 42481362 · doi:10.1016/j.neurol.2026.06.004
- [S12] Vilardo M, Mahler JV, Leles Vieira de Souza B, Salema Pascual G, Cardoso LJC, Veloso VD, et al. Effectiveness and Safety of Plasmapheresis in MOGAD Attacks: A Systematic Review and Meta-Analysis. Neurology. (2026). PubMed 42485605 · doi:10.1212/wnl.0000000000218300