Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Metastatic uveal melanoma and tebentafusp
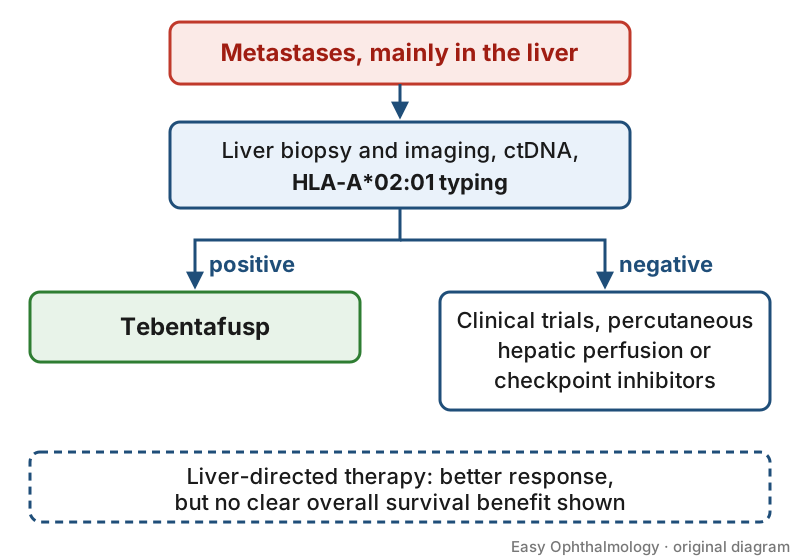
Metastatic uveal melanoma develops in approximately 20-30% of patients despite effective control of the primary tumour, mainly in the liver, and carries a poor prognosis [S8]. Tebentafusp is the first systemic drug shown to improve overall survival, but it can be used only in HLA-A*02:01-positive patients [S8] [S11].
Key points - In a phase 3 RCT, tebentafusp gave median overall survival of 21.6 versus 16.9 months with investigator's choice, and 5-year survival of 16% versus 8% [S11]. - HLA-A*02:01 typing is needed before tebentafusp; options are limited for HLA-negative patients [S8]. - Liver-directed therapies (isolated or percutaneous hepatic perfusion with melphalan) improve response and progression-free survival over best alternative care; a clear overall survival benefit has not been shown [S3] [S7]. - Immune checkpoint inhibitors have low response rates in uveal melanoma (pooled 5.6%), and dual therapy does better than single agents [S6]. - At current US pricing, tebentafusp was not cost-effective in one model [S4].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Liver involvement. About half of patients with metastatic disease present with isolated liver metastases, with median survival of 6-12 months [S3].
- Short survival without effective treatment. Across 2494 patients in a pooled analysis, median overall survival was 1.07 years, and most apparent differences between treatments were attributed to bias [S1].
- Tebentafusp toxicity. Cytokine-mediated and skin events are common; in the phase 3 trial rash occurred in 83%, pyrexia in 76% and pruritus in 69%, mostly in the first three or four doses [S2].
Recognise it
- Metastases occur mainly in the liver [S8] [S9].
- A significant proportion of patients treated definitively for the primary tumour eventually develop metastatic disease, which is why systemic surveillance is recommended [S9].
Confirm it
- French consensus guidelines recommend liver biopsy and imaging, circulating tumour DNA (ctDNA) analysis and high-definition HLA typing for HLA-A*02:01 [S8].
- Surveillance studies mostly recommend imaging at least every 6 months and MRI over ultrasound for higher-risk patients, but the evidence is of variable quality [S9].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Resource tiers: metastatic uveal melanoma is managed by medical oncology and specialist liver services, so Tier A / Tier B / Tier C advice is limited to recognising the risk and referring. Eye clinics at every tier should ensure patients treated for uveal melanoma are linked to systemic surveillance [S9].
Specialist oncology management
- Tebentafusp (HLA-A*02:01-positive). In the phase 3 trial (378 previously untreated patients), 1-year overall survival was 73% versus 59% with investigator's choice of pembrolizumab, ipilimumab or dacarbazine (HR 0.51) [S2]. At 5 years median overall survival was 21.6 versus 16.9 months (HR 0.67) [S11]. Benefit was seen even in patients whose best response was progressive disease, and undetectable or falling ctDNA was associated with longer survival [S11]. A meta-analysis of 997 patients in 12 cohorts gave median overall survival of 21.2 months and median progression-free survival of 3.9 months; the discontinuation rate was 2% [S10]. A propensity-weighted comparison also favoured tebentafusp over nivolumab plus ipilimumab (HR 0.52) [S5]. Dosing is not covered here; follow the product information and local protocols.
- Immune checkpoint inhibitors. Pooled data from 1414 patients: objective response 5.6%, median overall survival 11.2 months; dual therapy achieved better response (12.4% vs 3.4%) and overall survival (16.3 vs 9.8 months) than single agents [S6]. For HLA-A*02:01-negative patients with extensive disease, clinical trials, percutaneous hepatic perfusion or checkpoint inhibitors alone or combined can be proposed [S8].
- Isolated hepatic perfusion (IHP). In the SCANDIUM phase 3 RCT (87 patients with isolated liver metastases), IHP gave overall response of 40% versus 4.5% and median progression-free survival of 7.4 versus 3.3 months; there was one treatment-related death [S3].
- Percutaneous melphalan/hepatic delivery system. In a randomised study converted to single-arm because of slow enrolment, exploratory analyses favoured melphalan/HDS over best alternative care (median overall survival 18.5 vs 14.5 months), with serious adverse events in 51.2% versus 21.9%, mostly cytopenias [S7]. Dose as reported in [S7]: 3 mg/kg ideal body weight every 6 to 8 weeks for up to 6 cycles.
- Combined approaches. A network meta-analysis of 16 RCTs ranked liver-directed therapy combined with checkpoint inhibitors highest for overall and progression-free survival, with tebentafusp second for overall survival but worst for progression-free survival [S12]. This conflicts with the trial-based view of tebentafusp as standard first-line therapy [S8] [S11] and rests on indirect comparisons.
- Cost. A US model estimated an incremental cost-effectiveness ratio of $953 230 per QALY for tebentafusp, far above the $200 000 threshold [S4].
Refer when
| Situation | Urgency |
|---|---|
| Patient with treated uveal melanoma and new liver lesion, raised liver tests or new systemic symptoms | Urgent to medical oncology; timing per your local service or specialist advice |
| Treated patient not enrolled in any systemic surveillance | Routine, at the next clinic visit, to oncology for a surveillance plan |
Pitfalls
- Starting tebentafusp without HLA-A*02:01 typing [S8].
- Stopping tebentafusp only because of radiological progression: patients treated beyond progression lived longer in a post hoc analysis [S11].
- Reading higher response rates after liver-directed therapy as proof of longer survival [S7] [S12].
- Using cutaneous melanoma results for uveal melanoma: response to checkpoint inhibitors is much lower [S6].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2019 | Systematic review and pooled individual-level meta-analysis |
| [S2] | 2021 | Phase 3 RCT, primary analysis |
| [S3] | 2023 | Phase 3 RCT (SCANDIUM), secondary outcomes |
| [S4] | 2023 | Cost-effectiveness model (US payer) |
| [S5] | 2024 | Propensity-weighted comparison across trials |
| [S6] | 2024 | Meta-analysis, 41 cohorts |
| [S7] | 2025 | Randomised study amended to single-arm |
| [S8] | 2025 | French expert consensus guideline |
| [S9] | 2026 | Systematic review of surveillance |
| [S10] | 2026 | Meta-analysis of 12 cohorts |
| [S11] | 2026 | Phase 3 RCT, final 5-year analysis |
| [S12] | 2026 | Network meta-analysis of RCTs |
- The tebentafusp phase 3 trial was open-label and funded by Immunocore [S2].
- The control arm in the tebentafusp trial was mostly single-agent therapy; comparison with combined checkpoint inhibitors is indirect [S5].
- The melphalan/HDS efficacy results are exploratory only [S7].
- Not covered by these sources: tebentafusp dosing and monitoring schedule, MEK inhibitors and other targeted agents beyond the network meta-analysis, adjuvant therapy, access to these drugs in low- and middle-income countries, and evidence-based referral timings.
Related articles
- Uveal melanoma: diagnosis and primary treatment
- Ocular adverse events of immune checkpoint inhibitors and targeted cancer drugs
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Rantala ES, Hernberg M, Kivelä TT Overall survival after treatment for metastatic uveal melanoma: a systematic review and meta-analysis. Melanoma research. (2019). PubMed 30664106 · doi:10.1097/cmr.0000000000000575
- [S2] Nathan P, Hassel JC, Rutkowski P, Baurain JF, Butler MO, Schlaak M, et al. Overall Survival Benefit with Tebentafusp in Metastatic Uveal Melanoma. The New England journal of medicine. (2021). PubMed 34551229 · doi:10.1056/nejmoa2103485
- [S3] Olofsson Bagge R, Nelson A, Shafazand A, All-Eriksson C, Cahlin C, Elander N, et al. Isolated Hepatic Perfusion With Melphalan for Patients With Isolated Uveal Melanoma Liver Metastases: A Multicenter, Randomized, Open-Label, Phase III Trial (the SCANDIUM Trial). Journal of clinical oncology : official journal of the American Society of Clinical Oncology. (2023). PubMed 36940407 · doi:10.1200/jco.22.01705
- [S4] Luo S, Xie C, Lin N, Lin D, Gu D, Lin S, et al. Cost-effectiveness analysis of an orphan drug tebentafusp in patients with metastatic uveal melanoma and a call for value-based pricing. Melanoma research. (2023). PubMed 37650713 · doi:10.1097/cmr.0000000000000919
- [S5] Piulats JM, Watkins C, Costa-García M, Del Carpio L, Piperno-Neumann S, Rutkowski P, et al. Overall survival from tebentafusp versus nivolumab plus ipilimumab in first-line metastatic uveal melanoma: a propensity score-weighted analysis. Annals of oncology : official journal of the European Society for Medical Oncology. (2024). PubMed 38048850 · doi:10.1016/j.annonc.2023.11.013
- [S6] Yamada K, Takeuchi M, Fukumoto T, Suzuki M, Kato A, Mizuki Y, et al. Immune checkpoint inhibitors for metastatic uveal melanoma: a meta-analysis. Scientific reports. (2024). PubMed 38570507 · doi:10.1038/s41598-024-55675-5
- [S7] Zager JS, Orloff M, Ferrucci PF, Choi J, Eschelman DJ, Glazer ES, et al. An Open-label, Randomized Study of Melphalan/Hepatic Delivery System Versus Best Alternative Care in Patients with Unresectable Metastatic Uveal Melanoma. Annals of surgical oncology. (2025). PubMed 40192993 · doi:10.1245/s10434-025-17231-x
- [S8] Rodrigues M, Servois V, Mariani P, Pracht M, Dutriaux C, Grillet F, et al. Management of metastatic uveal melanoma: French expert consensus guidelines. Bulletin du cancer. (2025). PubMed 40628555 · doi:10.1016/j.bulcan.2025.05.011
- [S9] Zaman FY, Ghaus A, Shackleton M, Kee D, Joshua AM, O'Day R, et al. Systemic Surveillance Guidelines for Uveal Melanoma: A Systematic Review. Clinical & experimental ophthalmology. (2026). PubMed 40990144 · doi:10.1111/ceo.70002
- [S10] Saldanha EF, Noronha MM, Reis PCA, Passos PRC, Filho VOC, Cappellaro AP, et al. Tebentafusp in Metastatic Uveal Melanoma: A Meta-analysis. Targeted oncology. (2026). PubMed 41335285 · doi:10.1007/s11523-025-01187-9
- [S11] Piperno-Neumann S, Rutkowski P, Hassel JC, Butler MO, Schlaak M, Sullivan RJ, et al. Five-year survival with tebentafusp in metastatic uveal melanoma. Annals of oncology : official journal of the European Society for Medical Oncology. (2026). PubMed 42162665 · doi:10.1016/j.annonc.2026.05.695
- [S12] Chen Q, Zhou J, Zhou H, Wang H, Li J Comparative efficacy of therapeutic modalities for metastatic uveal melanoma: a systemic review and network meta-analysis. Frontiers in oncology. (2026). PubMed 42245738 · doi:10.3389/fonc.2026.1811719