Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Cytomegalovirus Retinitis
Cytomegalovirus retinitis (CMVR) is the most common ocular opportunistic infection in people with HIV and the leading cause of blindness in this group [S5]. It also occurs with transplantation, haematological malignancy and iatrogenic immunosuppression [S5]. In low- and middle-income countries it remains common in people presenting late with HIV, and almost a third have vision loss [S2].
Key points - Diagnosis is clinical: a susceptible, immunocompromised patient with characteristic fundus findings; intraocular fluid PCR is used when confirmation is needed [S10]. - Oral valganciclovir is the preferred first-line treatment, with intravitreal ganciclovir when CMVR threatens the posterior pole (2025 international consensus) [S10]. - Antiretroviral therapy (ART) matters: recurrence was 10% in ART-treated vs 33% in untreated HIV patients [S9]. - Routine retinal screening of late-presenting HIV patients should be considered; CD4 count was below 50 cells/µL in 73.4% of cases where reported [S2]. - Immune recovery uveitis must be distinguished from CMVR relapse [S10].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Lesion approaching the posterior pole. Indication for intravitreal ganciclovir [S10].
- CD4 count below 50 cells/µL. Present in 73.4% of CMVR cases where reported [S2].
- Retinal detachment. Occurred in a pooled 11% of treated patients [S9]; ultra-widefield photography helps detect early retinal breaks [S11].
- New inflammation after starting ART. Immune reconstitution inflammatory syndrome developed in 37.7% of patients with prior CMVR [S1]; immune recovery uveitis must be separated from relapse [S10].
- Neutropenia on ganciclovir. The most reported adverse effect, up to 50% [S9].
Recognise it
- Who. People with advanced HIV/AIDS [S9]; also non-HIV patients ranging from limited immune dysfunction (advanced age, diabetes) to haematological and rheumatological disease, and local ocular immunosuppression [S4].
- Burden. Pooled prevalence in Asia was 14.0% of HIV-positive adults examined, with no clear decline between 1993-2002 and 2009-2013 [S2]. In Africa, CMVR was found in 0% to 2.6% of examined HIV-infected individuals, and CMV seroprevalence exceeded 90% in most populations [S3].
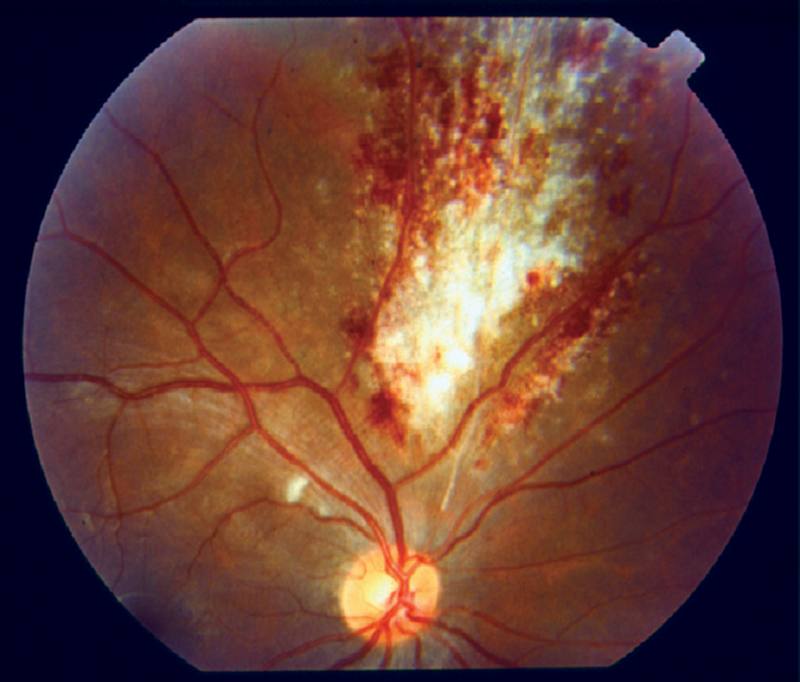
- Signs. CMVR may be asymptomatic at first; relatively mild vitreous inflammation helps distinguish it from other diseases in HIV [S8]. It usually starts in the peripheral retina and advances toward the posterior pole, with central necrosis and intraretinal haemorrhage giving the "pizza pie" appearance [S8].
Confirm it
- Clinical examination and colour fundus photography are the primary methods for diagnosis and follow-up; ultra-widefield photography detects peripheral and satellite lesions [S11].
- OCT shows inner retinal necrosis and complications such as cystoid macular oedema and epiretinal membrane; autofluorescence outlines the advancing edge and healed lesions [S11]. OCT angiography and ICGA have limited roles [S11].
- Intraocular fluid PCR when confirmation is necessary [S10].
- Screening in resource-limited regions: fundus photography, CD4 count and telemedicine can be used [S8]; telemedicine and AI-aided interpretation may reduce screening resource needs [S10].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Ensure people with HIV are on ART; ART-treated patients had fewer recurrences [S9]. IRIS risk is highest when ART starts with CD4 below 50 cells per microL, and might be reduced by starting ART before immunodeficiency becomes advanced [S1].
- Refer late-presenting HIV patients for retinal screening, especially with low CD4 count [S2] (timing in the table below).
Tier B (general eye clinic)
- Screen high-risk patients with dilated fundoscopy or fundus photography [S2] [S10].
- Start antiviral treatment early; it significantly reduces the risk of vision loss [S8]. Oral valganciclovir is preferred first-line [S10]. Doses are not covered by these abstracts: follow national HIV guidelines and local formularies.
- Monitor blood counts for neutropenia [S9].
- Coordinate with the HIV programme so ART is started or optimised; HIV programmes must be able to manage late presenters [S2].
Tier C (specialist centre)
- Intravitreal ganciclovir when the posterior pole is threatened [S10]. In pooled data, inflammation resolution tended to be higher with intravitreal than intravenous antivirals (88% vs 75%, not significant) [S9].
- Outcomes to expect. Across 59 studies (4,501 patients): inflammation resolution 90%, visual acuity improvement 18%, recurrence 19%, retinal detachment 11% [S9].
- Stopping maintenance. Can be considered after 6 months of inactive CMVR with immune reconstitution [S10].
- Immune recovery uveitis. No definite diagnostic criteria or standardised treatment exist; timing of antiviral and ART initiation is a complex decision [S7].
- Second-line options. Novel antivirals and immunotherapies, such as CMV-specific adoptive T-cell therapy and CMV immunoglobulin, are emerging [S8] [S10].
- Non-HIV patients. Treatment strategy still lacks consensus [S4].
Refer when
| Situation | Urgency |
|---|---|
| Suspected CMVR near the macula or optic disc | Same-day to a service able to give intravitreal ganciclovir [S10] |
| Suspected peripheral CMVR, or new floaters or field loss in advanced HIV | Emergency, within 24 hours, eye assessment [S8] [EIC expert opinion] |
| Late-presenting HIV patient, especially CD4 below 50 cells/µL | Routine retinal screening at presentation to HIV care [S2] |
Pitfalls
- Assuming CMVR has disappeared in the ART era in low- and middle-income settings [S2].
- Missing asymptomatic early disease without screening [S8].
- Mistaking immune recovery uveitis for relapse, or relapse for immune recovery uveitis [S10].
- Overlooking CMVR in HIV-negative immunosuppressed patients, including those with local ocular immunosuppression [S4].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2010 | Meta-analysis of 54 cohort studies (IRIS) |
| [S2] | 2013 | Systematic review and meta-analysis, 65 studies in LMICs |
| [S3] | 2017 | Systematic review, Africa |
| [S4] | 2018 | Narrative review, HIV-negative CMVR |
| [S5] | 2019 | Narrative review |
| [S6] | 2020 | Narrative review, global HIV ocular disease |
| [S7] | 2024 | Narrative review, immune recovery uveitis |
| [S8] | 2024 | Narrative review |
| [S9] | 2025 | Meta-analysis, 59 studies |
| [S10] | 2025 | International consensus (Asia-Pacific societies) |
| [S11] | 2026 | Imaging consensus (MUV task force) |
- There are no established treatment guidelines from trial evidence; the antiviral meta-analysis pooled varied, mostly non-comparative regimens [S9].
- Widespread ART has reduced CMVR [S5] [S6], but LMIC data show persistently high prevalence in late presenters [S2]; the two pictures differ by setting.
- Not covered by these sources: drug doses, intravitreal injection schedules, foscarnet and cidofovir specifics, congenital CMV, and paediatric disease.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Müller M, Wandel S, Colebunders R, Attia S, Furrer H, Egger M, et al. Immune reconstitution inflammatory syndrome in patients starting antiretroviral therapy for HIV infection: a systematic review and meta-analysis. The Lancet. Infectious diseases. (2010). PubMed 20334848 · doi:10.1016/s1473-3099(10)70026-8
- [S2] Ford N, Shubber Z, Saranchuk P, Pathai S, Durier N, O'Brien DP, et al. Burden of HIV-related cytomegalovirus retinitis in resource-limited settings: a systematic review. Clinical infectious diseases : an official publication of the Infectious Diseases Society of America. (2013). PubMed 23899681 · doi:10.1093/cid/cit494
- [S3] Grønborg HL, Jespersen S, Hønge BL, Jensen-Fangel S, Wejse C Review of cytomegalovirus coinfection in HIV-infected individuals in Africa. Reviews in medical virology. (2017). PubMed 27714898 · doi:10.1002/rmv.1907
- [S4] Shapira Y, Mimouni M, Vishnevskia-Dai V Cytomegalovirus retinitis in HIV-negative patients - associated conditions, clinical presentation, diagnostic methods and treatment strategy. Acta ophthalmologica. (2018). PubMed 29068151 · doi:10.1111/aos.13553
- [S5] Munro M, Yadavalli T, Fonteh C, Arfeen S, Lobo-Chan AM Cytomegalovirus Retinitis in HIV and Non-HIV Individuals. Microorganisms. (2019). PubMed 31905656 · doi:10.3390/microorganisms8010055
- [S6] Peters RPH, Kestelyn PG, Zierhut M, Kempen JH The Changing Global Epidemic of HIV and Ocular Disease. Ocular immunology and inflammation. (2020). PubMed 32396027 · doi:10.1080/09273948.2020.1751214
- [S7] Dionson MM Immune recovery uveitis: an ocular manifestation in HIV/AIDS receiving treatment. Current opinion in ophthalmology. (2024). PubMed 39046420 · doi:10.1097/icu.0000000000001078
- [S8] Zhang J, Kamoi K, Zong Y, Yang M, Zou Y, Miyagaki M, et al. Cytomegalovirus Retinitis: Clinical Manifestations, Diagnosis and Treatment. Viruses. (2024). PubMed 39339903 · doi:10.3390/v16091427
- [S9] Putera I, La Distia Nora R, Dewi AC, Suhada DS, Cifuentes-González C, Rojas-Carabali W, et al. Antiviral therapy for cytomegalovirus retinitis: A systematic review and meta-analysis. Survey of ophthalmology. (2025). PubMed 39549781 · doi:10.1016/j.survophthal.2024.11.004
- [S10] Hwang DK, Ng DSC, Qian Z, Agrawal R, Chan ASY, Chhablani J, et al. International consensuses and guidelines on diagnosing and managing cytomegalovirus (CMV) retinitis by the Asia-Pacific Vitreo-retina Society (APVRS), the Asia-Pacific Professors of Ophthalmology (AAPPO) and the Asia-Pacific Society of Ocular Inflammation and Infection (APSOII). Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2025). PubMed 41038280 · doi:10.1016/j.apjo.2025.100248
- [S11] Leal I, Agarwal A, Berkenstock M, Sonoda KH, Dodds E, Kempen JH, et al. Evidence and Consensus-Based Imaging Guidelines in Cytomegalovirus Retinitis: Multimodal Imaging in Uveitis (MUV) Task Force - Report 15. Ophthalmology. Retina. (2026). PubMed 42119730 · doi:10.1016/j.oret.2026.05.004