Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Acute Primary Angle Closure
Acute primary angle closure (APAC) is an eye emergency in which intraocular pressure (IOP) can reach 50 mmHg or more [S3]. Treatment aims to lower IOP within hours and then open the angle definitively, and in a 10-year follow-up of a randomised trial four eyes treated with laser iridotomy alone became blind [S6].
Key points - Medical therapy, anterior chamber paracentesis and laser iridoplasty are used in sequence to break the attack; in one RCT 92.20% of eyes were controlled by 6 hours with this approach [S12]. - Immediate paracentesis lowered IOP faster and gave better visual acuity than medical treatment alone in a small RCT [S3]. - In eyes with APAC and cataract, early phacoemulsification gave better IOP control than laser peripheral iridotomy (LPI) at 2 years [S2] and less medication, fewer synechiae and less blindness at 10 years [S6]. - Topiramate can cause acute angle closure, with onset peaking about 2 weeks after starting the drug; stopping it plus medical therapy resolved most cases [S9]. - When medicine fails, phacoemulsification with goniosynechialysis (phaco-GSL) and phacotrabeculectomy both controlled IOP in a Vietnamese multicentre RCT, with fewer complications after phaco-GSL [S7].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- IOP of 50 mmHg or more with reduced vision and pain [S3].
- Corneal oedema, ciliary flush and a non-reactive pupil [S3] [S5].
- Attack not controlled by medical therapy (refractory APAC): surgery is needed [S7] [S10].
- A patient started on topiramate in the last weeks who develops eye symptoms: in reported cases the mean time to onset was 14.1 days [S9].
- Recent pupil dilation in an eye with narrow angles: 0.64% of narrow-angle subjects developed acute angle closure within 6 hours of tropicamide despite oral acetazolamide [S1].
Recognise it: features and risk factors
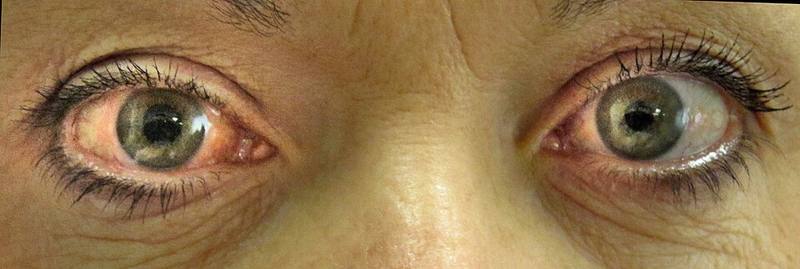
- Symptoms and signs measured in trials include pain, reduced visual acuity, corneal oedema, conjunctival erythema, ciliary flush and photophobia [S3] [S5].
- Anatomy. Primary angle-closure glaucoma is associated with a shallower anterior chamber, shorter axial length, more hyperopic refraction and cataract (OR 3.77) [S11].
- Drugs. Short-term antidepressant exposure was associated with acute angle closure (OR 1.36) [S11]. Topiramate-induced cases were mostly women (75.3%) with a mean age of 34.88 years, usually treated for migraine [S9]. These patients were younger than those in APAC trials (mean age 66.0 years in [S2]) [S9].
- Dilation. The risk of an acute attack after dilation with tropicamide in Asian narrow-angle subjects was low (0.64%), and a narrower gonioscopic angle was the only clinical predictor of an IOP rise [S1].
Confirm it
- Measure IOP; trials used Goldmann applanation tonometry and gonioscopy [S1] [S2].
- Examine the fellow eye; narrow angles on gonioscopy predict IOP rise after dilation [S1].
- Anterior segment OCT shows the angle widening after treatment and is a research tool for comparing treatments [S4]. It is not required to make the diagnosis.
Manage it
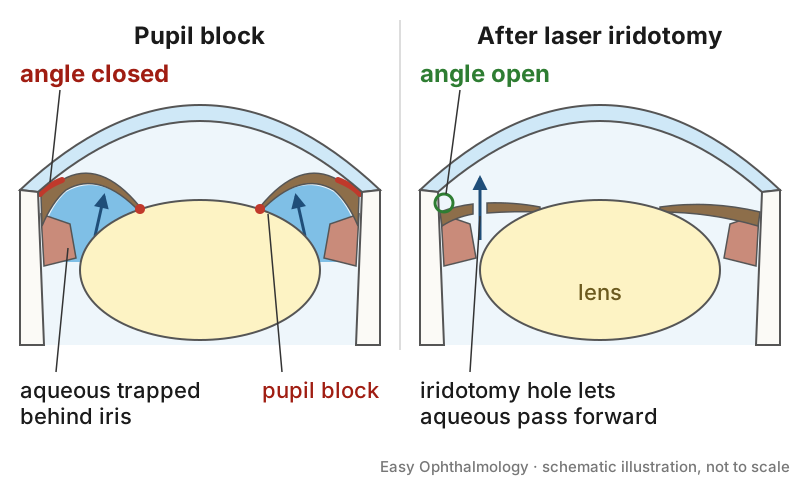
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Recognise the red flags and refer immediately to an eye unit.
- If the patient takes topiramate, the drug was stopped in every reported case of topiramate-induced closure [S9]; contact the prescriber.
- Dosing of IOP-lowering drugs is not covered by these sources; follow local formularies and protocols.
Tier B (general eye clinic)
- Medical therapy first. Systemic carbonic anhydrase inhibitors, hyperosmotic agents and steroids were used alongside topical therapy in 66.2% of topiramate cases [S9]. In one RCT, adding a single dose of timolol to sequential treatment did not improve IOP reduction, remission rate or time to relief [S12].
- Subconjunctival dexamethasone. Adding 2.5 mg subconjunctival dexamethasone (as reported in [S5]) to standard drugs gave lower IOP at 24 hours and a higher 24-hour success rate (79.7% vs 54.9%), with less ciliary flush and pain, in an RCT of 42 patients [S5].
- Anterior chamber paracentesis. In an RCT of eyes with IOP of 50 mmHg or more, paracentesis plus medical treatment lowered IOP faster at 15 minutes to 1 hour, reduced pain at 1 to 2 hours and gave better final visual acuity (0.43 vs 0.74 logMAR) [S3].
- Laser iridoplasty. Argon laser peripheral iridoplasty widened the angle more than medical therapy at 1 hour in a randomised study of 30 patients [S4]. In a sequential protocol of drugs, paracentesis and iridoplasty, 91.46% to 92.20% of eyes were controlled at 6 hours [S12].
- Laser peripheral iridotomy. After LPI, an IOP spike at 1 hour occurred in 6% to 9.8% of eyes; a review recommends checking IOP at 1 hour in patients with hyphaema, pigment dispersion, high pre-treatment IOP, thick irides or optic nerve damage [S8].
Tier C (specialist centre)
- APAC with cataract. Phacoemulsification within 1 week gave 2-year IOP control survival of 89.5% vs 61.1% with LPI [S2]. At 10 years, the phaco group used less medication, had less synechial closure and had no blindness, against 4 blind eyes in the LPI group [S6].
- Refractory APAC with cataract. Phaco-GSL and unaugmented phacotrabeculectomy both controlled IOP at 1 year, but complications in the first 3 months were 14.3% vs 62.2%, and visual acuity was better after phaco-GSL [S7].
- Refractory APAC without significant cataract. Laser iridoplasty followed by surgical iridectomy and trabeculectomy gave similar 1-year success (97.1% vs 92.6% complete success), with more early complications after iridoplasty plus iridectomy (45.9% vs 33.3%) [S10].
Refer when
| Situation | Urgency |
|---|---|
| Suspected APAC at any level without an eye specialist | Immediate transfer to an eye unit |
| APAC not controlled by medical therapy | Same-day referral to a centre able to operate [S7] [S10] |
| APAC controlled, with cataract | Within a week for lens extraction, as performed in [S2] |
| Fellow eye with narrow angle after an attack | Urgent for gonioscopy and laser; timing per your local service or specialist advice |
Pitfalls
- Relying on extra timolol to rescue a failing protocol [S12].
- Treating APAC with cataract by LPI alone and not offering lens extraction [S2] [S6].
- Missing drug causes such as topiramate in young patients [S9] or antidepressants [S11].
- Skipping the 1-hour IOP check after LPI in eyes with risk factors [S8].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | Prospective study within a trial, 471 narrow-angle subjects, Singapore |
| [S2] | 2012 | RCT, 37 patients |
| [S3] | 2013 | RCT, 54 patients |
| [S4] | 2016 | Randomised study, 30 patients |
| [S5] | 2020 | RCT, 42 patients |
| [S6] | 2021 | 10-year follow-up of an RCT, 40 of 62 patients examined |
| [S7] | 2021 | Multicentre RCT, 79 eyes, Vietnam |
| [S8] | 2021 | Literature review with recommendations |
| [S9] | 2022 | Systematic review of 77 case reports |
| [S10] | 2023 | RCT, 67 eyes, Vietnam |
| [S11] | 2023 | Meta-analysis of 45 observational studies |
| [S12] | 2025 | Double-blind RCT, China |
- All trials are small and single-country, mostly East and Southeast Asian; generalisability to other populations is limited [S8].
- The 10-year follow-up examined only 64.5% of patients, and 71.4% of the LPI group had already had lens extraction [S6].
- The topiramate evidence is case reports only [S9]; the antidepressant link is observational [S11].
- Not covered by these sources: doses and choice of acetazolamide, mannitol, glycerol and pilocarpine; time windows for transfer; management of the fellow eye; non-pupillary-block mechanisms.
Related articles
- Primary Angle-Closure Disease: Suspects to Glaucoma
- Gonioscopy and anterior-segment imaging of the angle
- The red eye: triage
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Lavanya R, Baskaran M, Kumar RS, Wong HT, Chew PT, Foster PJ, et al. Risk of acute angle closure and changes in intraocular pressure after pupillary dilation in Asian subjects with narrow angles. Ophthalmology. (2012). PubMed 22118999 · doi:10.1016/j.ophtha.2011.08.033
- [S2] Husain R, Gazzard G, Aung T, Chen Y, Padmanabhan V, Oen FT, et al. Initial management of acute primary angle closure: a randomized trial comparing phacoemulsification with laser peripheral iridotomy. Ophthalmology. (2012). PubMed 22885123 · doi:10.1016/j.ophtha.2012.06.015
- [S3] Yang X, Su W, Wang M, Bai Y, Li Y, Ge J, et al. Effect of anterior chamber paracentesis on initial treatment of acute angle closure. Canadian journal of ophthalmology. Journal canadien d'ophtalmologie. (2013). PubMed 24314422 · doi:10.1016/j.jcjo.2013.04.012
- [S4] Sng CC, Aquino MC, Liao J, Zheng C, Ang M, Chew PT Anterior segment morphology after acute primary angle closure treatment: a randomised study comparing iridoplasty and medical therapy. The British journal of ophthalmology. (2016). PubMed 26294102 · doi:10.1136/bjophthalmol-2015-307087
- [S5] Huang W, Li X, Gao K, Zhang X Combined subconjunctival injection of dexamethasone for the management of acute primary angle closure: a randomised controlled trial. The British journal of ophthalmology. (2020). PubMed 31000508 · doi:10.1136/bjophthalmol-2018-313473
- [S6] Chan PP, Tang FY, Leung DY, Lam TC, Baig N, Tham CC Ten-Year Clinical Outcomes of Acute Primary Angle Closure Randomized to Receive Early Phacoemulsification Versus Laser Peripheral Iridotomy. Journal of glaucoma. (2021). PubMed 33769358 · doi:10.1097/ijg.0000000000001799
- [S7] Nguyen Xuan H, Nguyen Dinh N, Nguyen Thu H, Nguyen Van C, Aung T, Loo Y, et al. Comparing the Safety and Efficacy of Phacogoniosynechialysis With Phacotrabeculectomy in the Management of Refractory Acute Primary Closure Angle Glaucoma With Cataract: A Multicenter Randomized Trial. Journal of glaucoma. (2021). PubMed 34008525 · doi:10.1097/ijg.0000000000001868
- [S8] Rozon JP, Des Marchais B Recommendations for intraocular pressure measurement one hour after laser peripheral iridotomy: Review of the literature. Journal francais d'ophtalmologie. (2021). PubMed 34565658 · doi:10.1016/j.jfo.2021.04.014
- [S9] Al Owaifeer AM, AlSultan ZM, Badawi AH Topiramate-induced acute angle closure: A systematic review of case reports and case series. Indian journal of ophthalmology. (2022). PubMed 35502014 · doi:10.4103/ijo.ijo_2134_21
- [S10] Nguyen HX, Nguyen ND, Nguyen HT, Fan KR, Vo HT, Nguyen CV, et al. Comparing combined laser iridoplasty and surgical iridectomy with trabeculectomy in treatment of refractory acute primary angle closure without significant cataract: a randomized controlled trial. Eye (London, England). (2023). PubMed 36402857 · doi:10.1038/s41433-022-02311-z
- [S11] Wang Y, Dong XX, Hou XW, Pan CW Risk Factors for Primary Angle-closure Glaucoma: A Systematic Review and Meta-analysis of 45 Studies. Optometry and vision science : official publication of the American Academy of Optometry. (2023). PubMed 37747945 · doi:10.1097/opx.0000000000002050
- [S12] Chen G, Wang J, Li K Efficacy and Tolerability of Single-Dose Timolol Eye Drops in the Sequential Treatment of Acute Angle-Closure Crisis: A Double-Blind, Randomized, Placebo-Controlled Trial. Clinical therapeutics. (2025). PubMed 40399148 · doi:10.1016/j.clinthera.2025.04.005